
City mobile crisis
Dispatch CAT teams from a live board, keep field status on phones, and place into local beds or programs without a side spreadsheet.
Respondr.care starts at the 988 or local crisis line — intake, CAT dispatch, and field status on one episode — then continues the same person into a bed, a SUD stay, or care coordination when the curb is not the end.
For city, county, and state teams running Crisis Now and 988 mobile crisis
≤ 5 min
Assign SLA to CAT
100%
Actions audit-logged
24/7
Crisis line coverage
988
Aligned intake workflows
One intake-to-CAT thread for 988 and local crisis lines — and the bed, SUD, and care coordination teams that continue the same person after the curb.
Dispatch CAT teams from a live board, keep field status on phones, and place into local beds or programs without a side spreadsheet.
Coordinator intake, SLA on assign and response, 72-hour follow-ups, closed-loop bed and SUD placement, and supervisor queues for Crisis Now / 988-aligned operations. See state pages.
Shared case records, team chat, and audit trails so multiple jurisdictions stay on the same person from first contact through stay and care coordination.
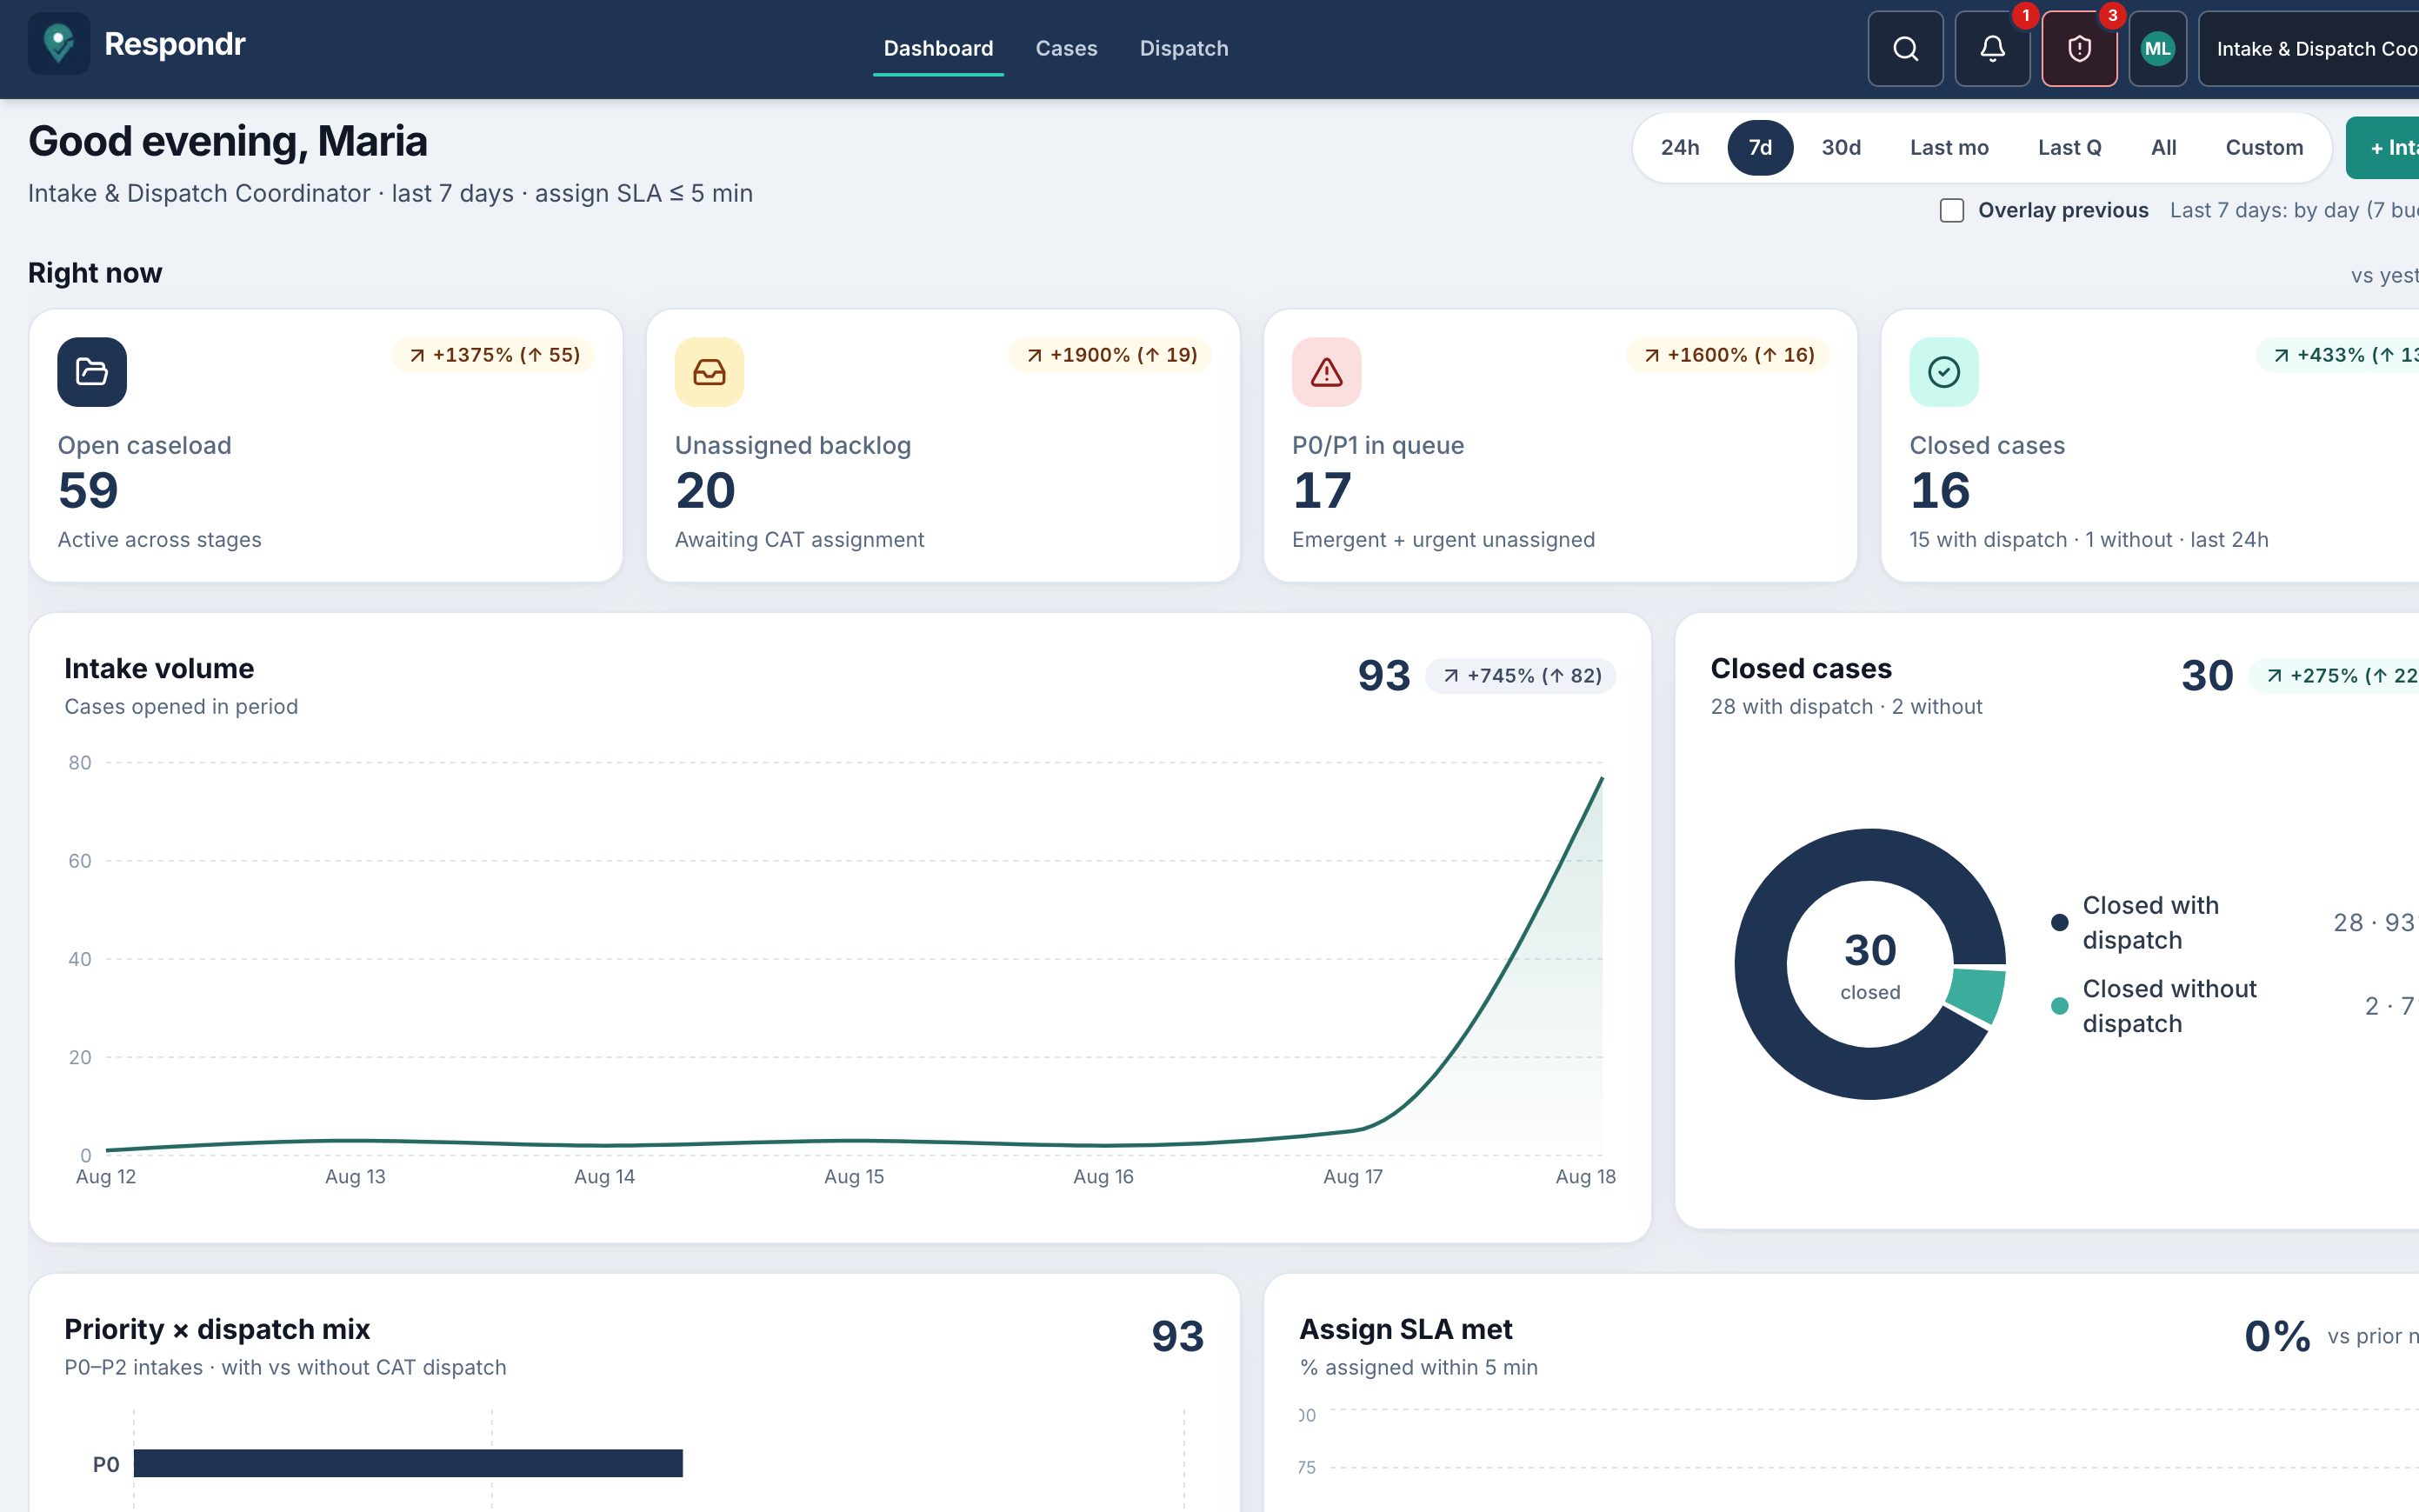
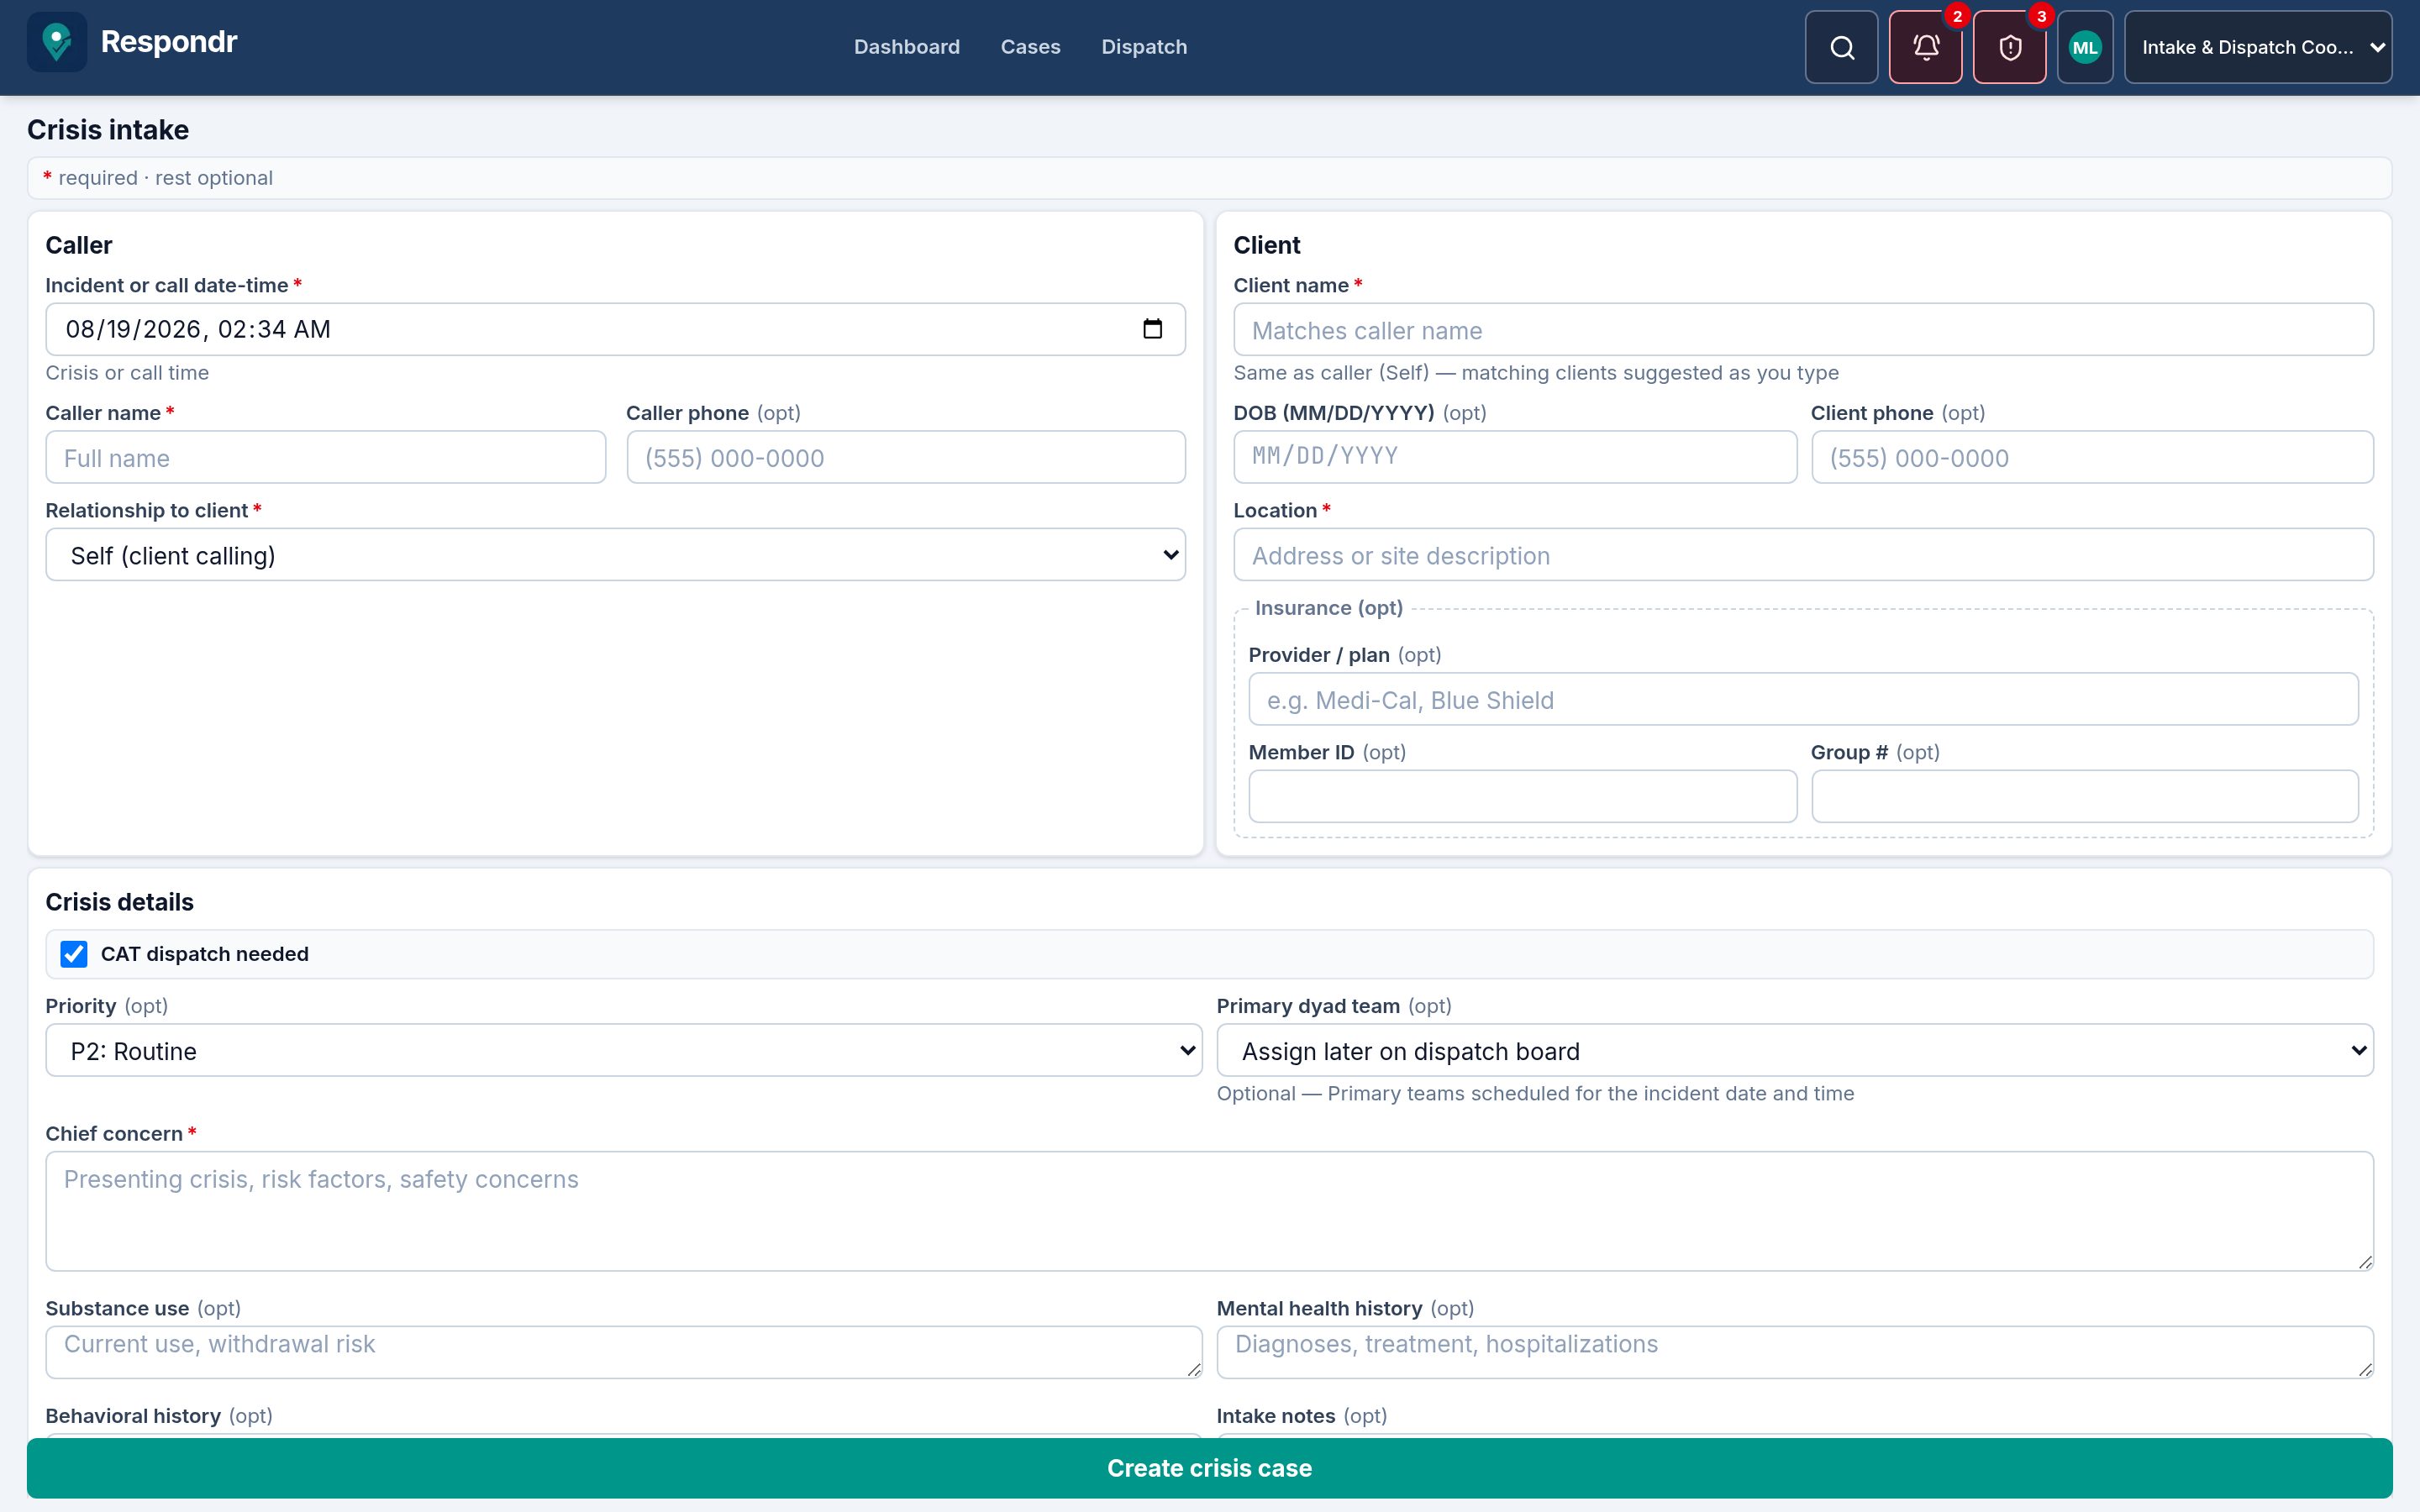
Crisis response time is mostly waiting: a P0 sitting unassigned, a CAT team that has not accepted, a case that has not moved in a day. The dashboard makes those waits countable so coordinators assign inside the five-minute SLA, CAT clears follow-ups before they go overdue, and supervisors spot stale cases and thin coverage before the next 988 call.
Most delay happens before a CAT team is on the case. Coordinators see who is waiting right now — and which of those waits are emergent — so the next assign is the one that shortens response, not the one that happened to be at the top of a list.
Intake → CAT assigned has a five-minute target. Assign → arrived is the Crisis Now-style two-hour proxy. Overlay the prior window so a slow week is a number on the board, not a story told after the shift.
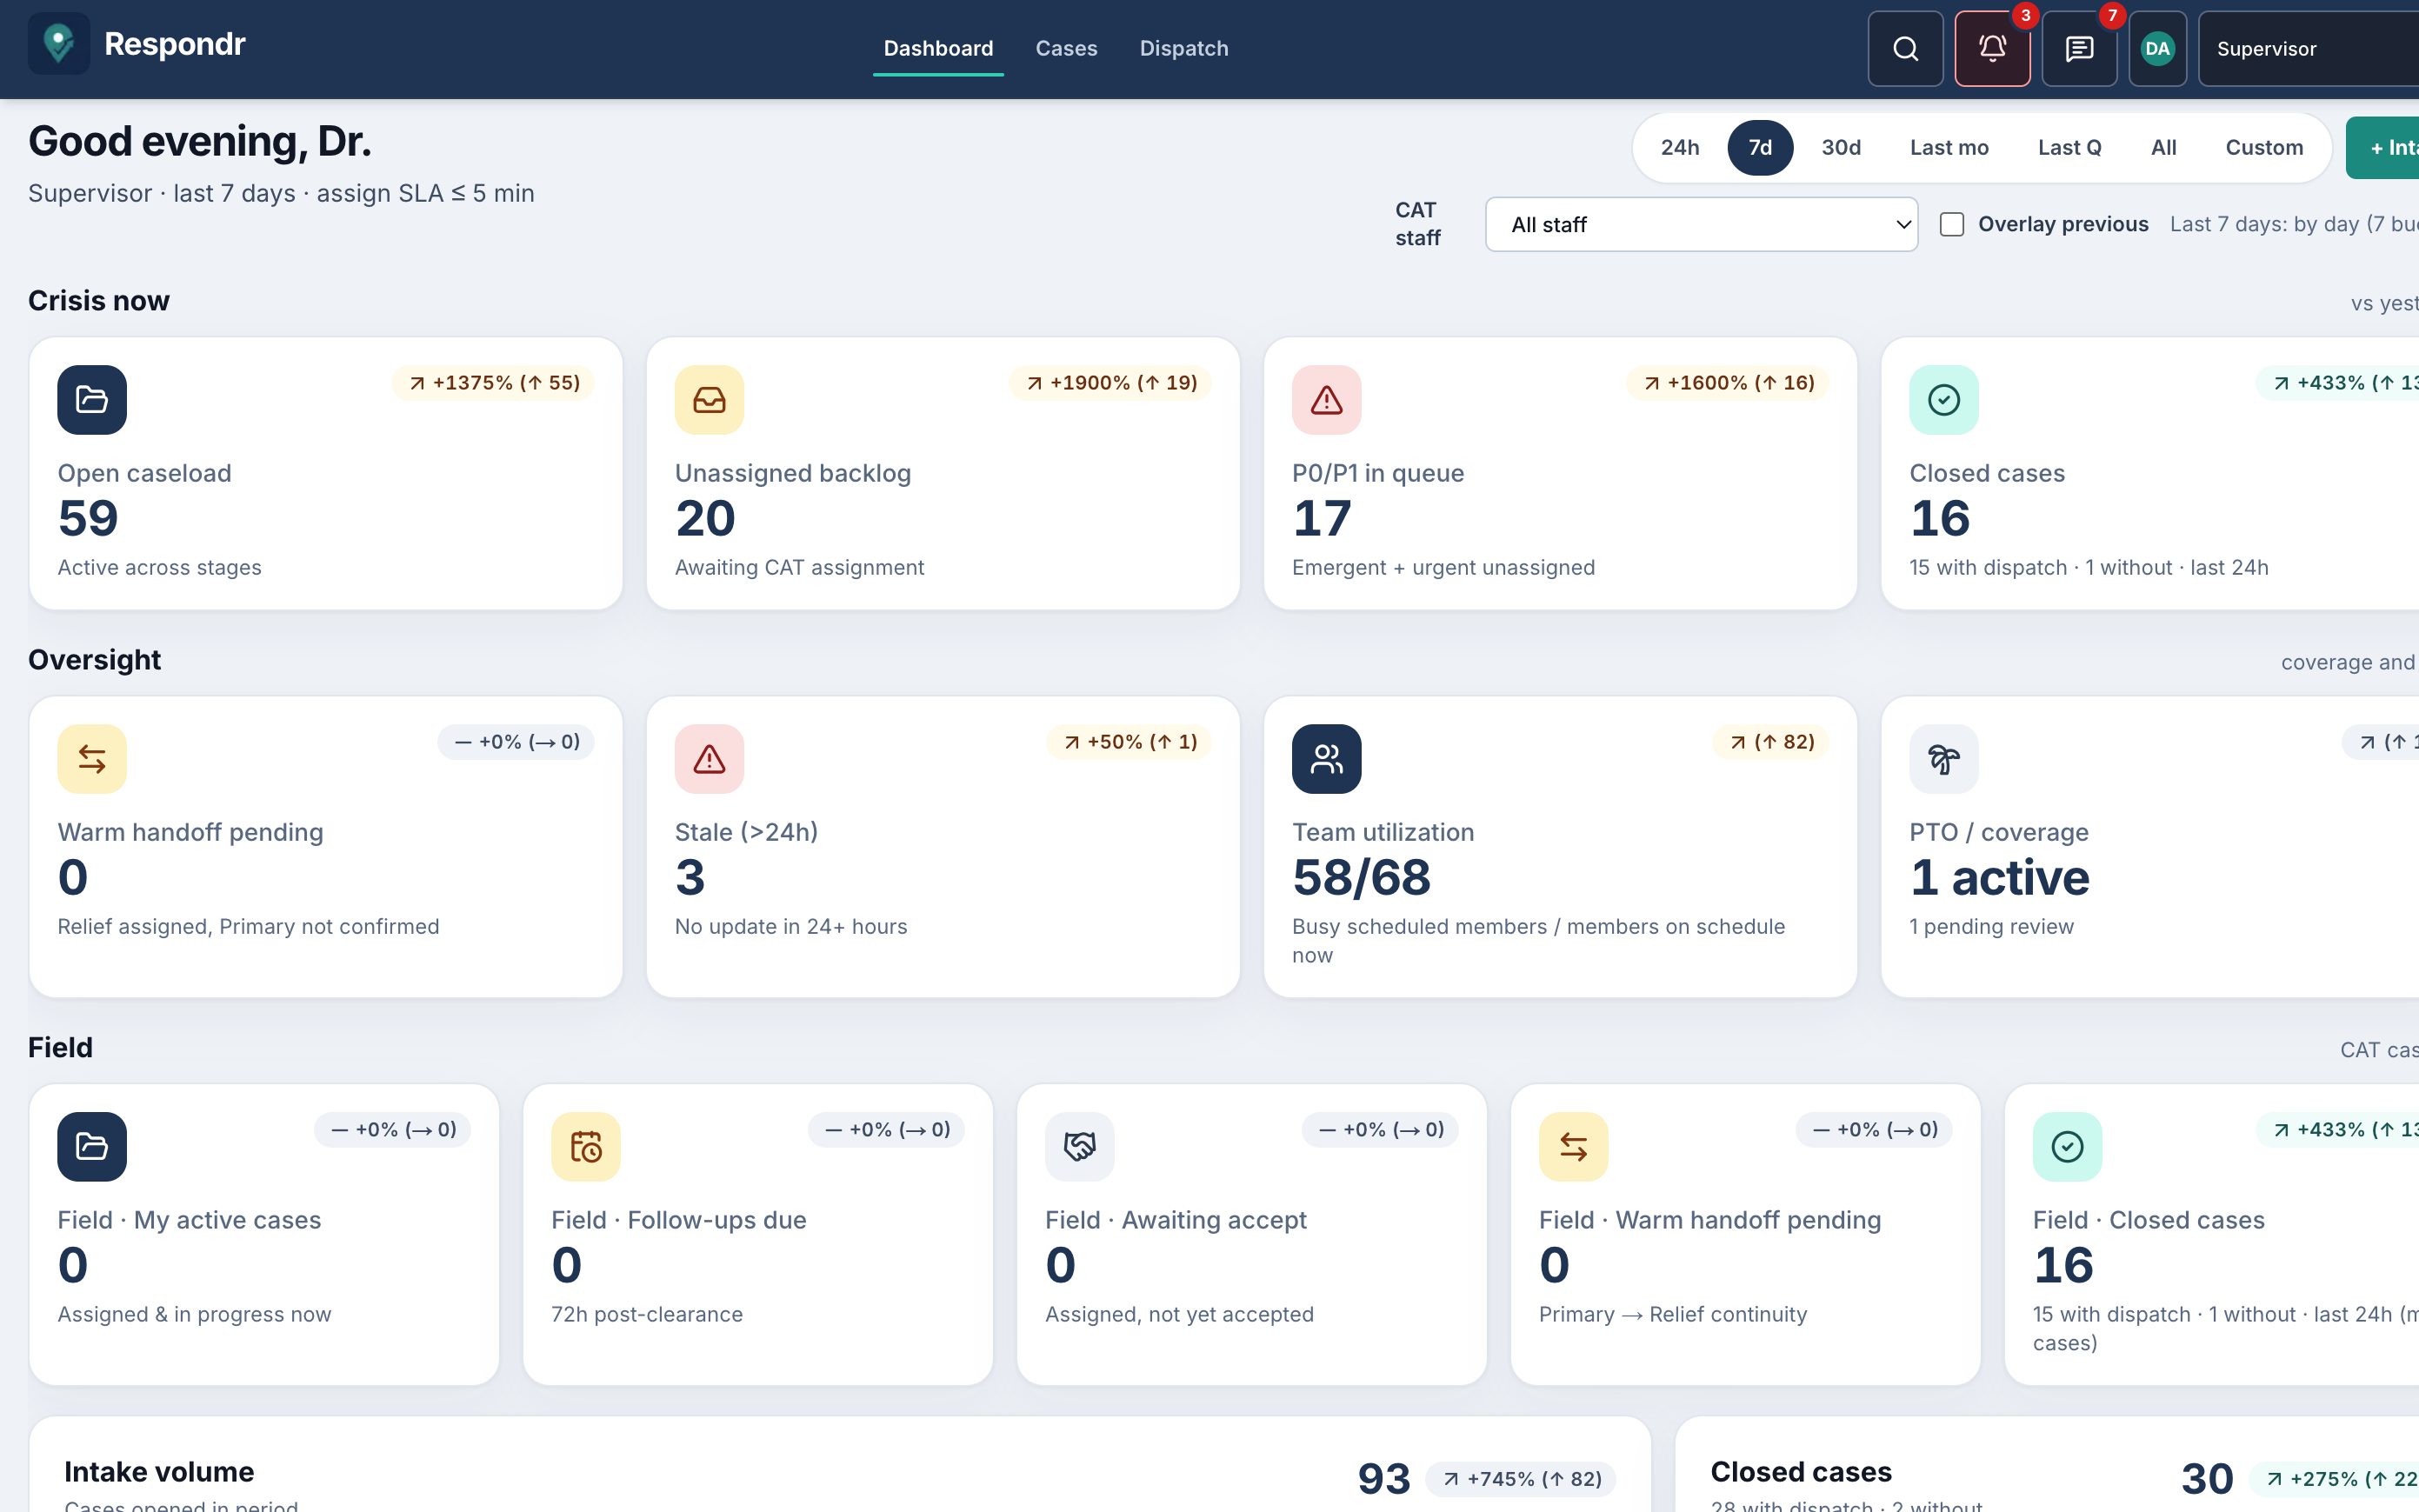
Supervisors see cases silent for 24+ hours and whether scheduled staff are already on scene. CAT sees follow-ups due so clearance is not the last contact. Aging and thin coverage are how a fast first assign still fails the person.
CAT in the field
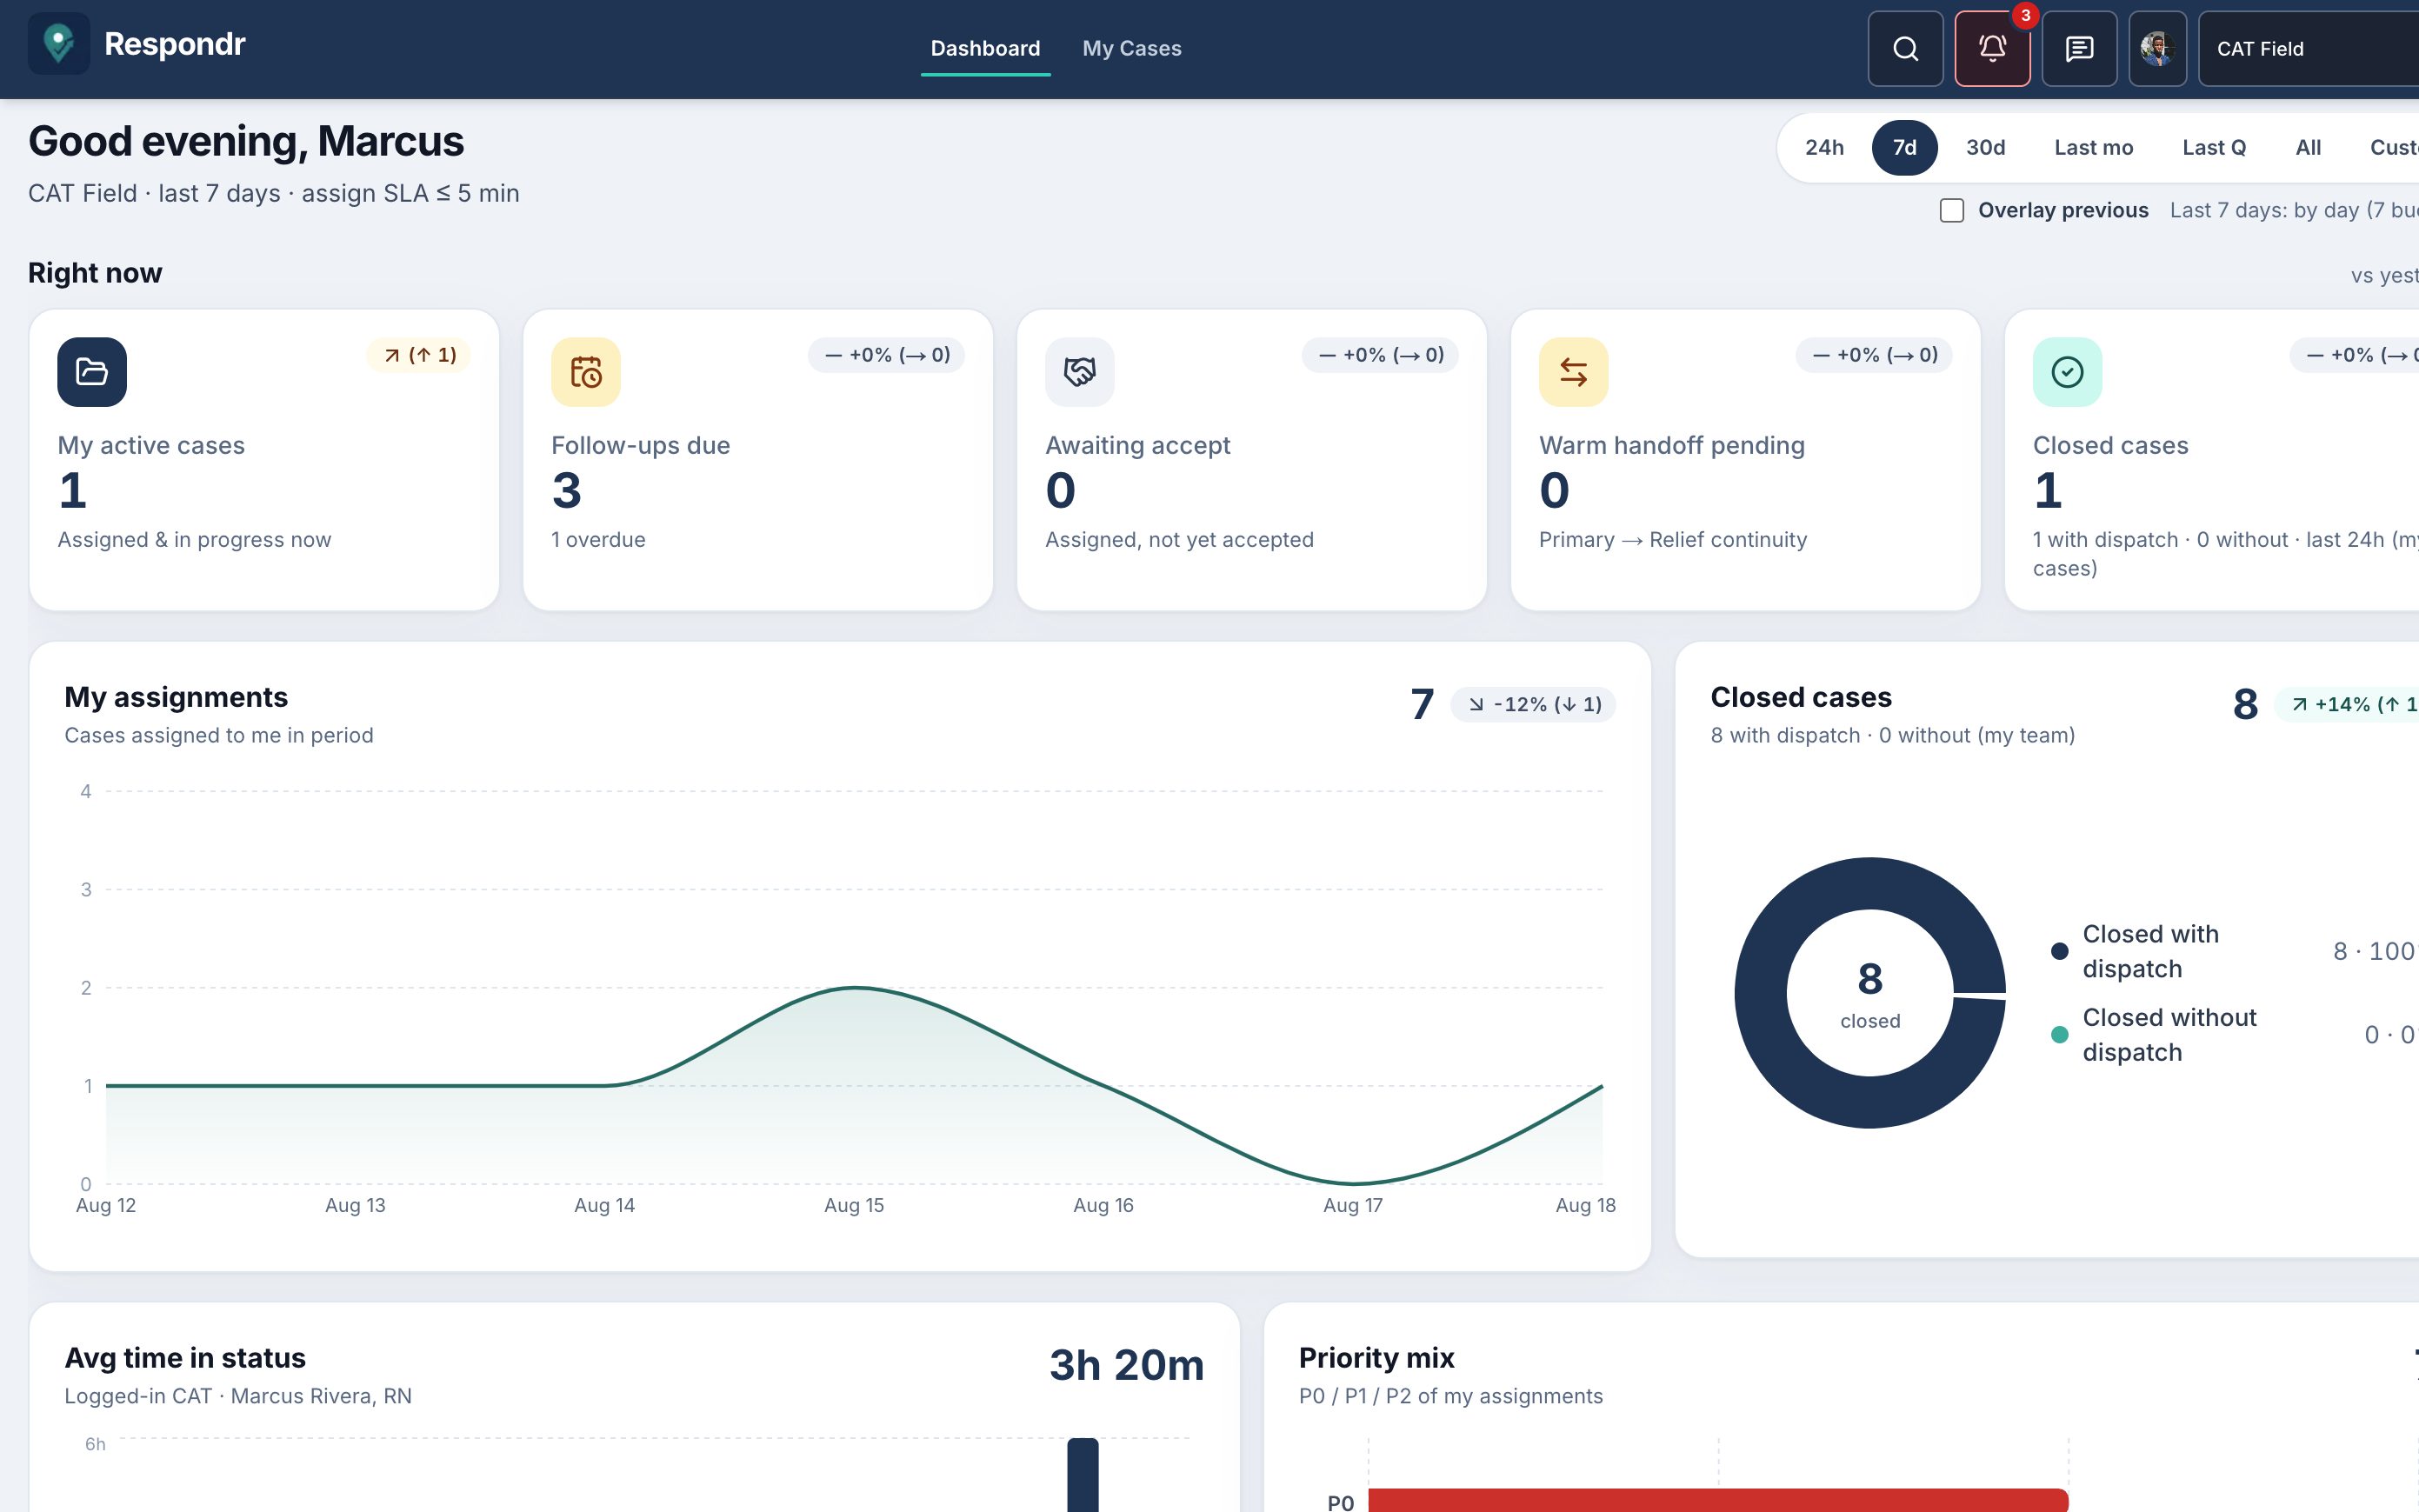
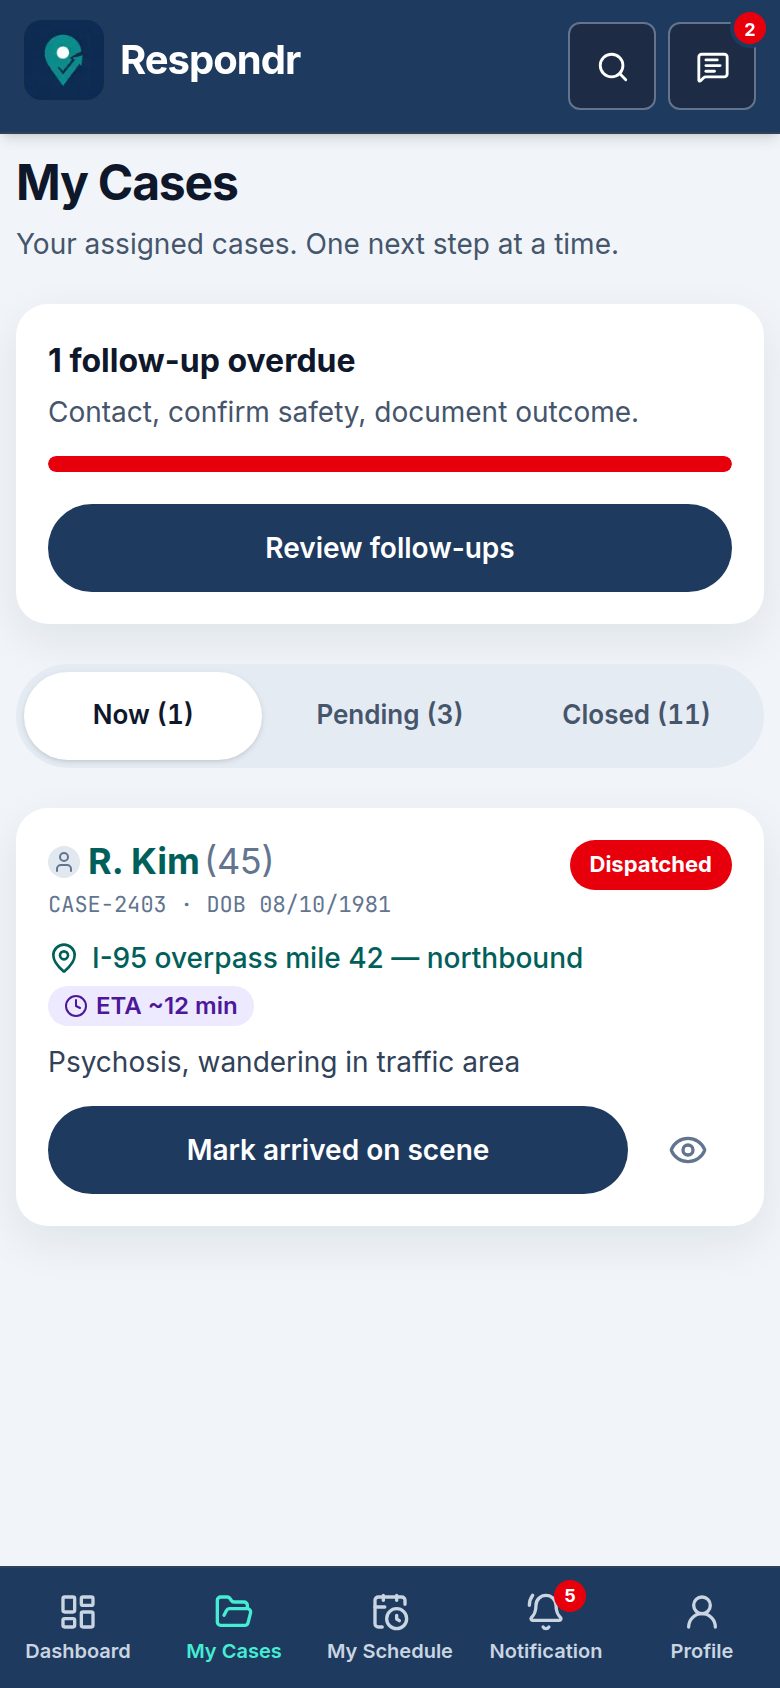
CAT My Cases is a quieter, large-tap field home. Phone layout is a single column. Tablet layout is a two-column case grid. When a member accepts assignment, teammates see an ETA next to the incident pin and a map of the scene.
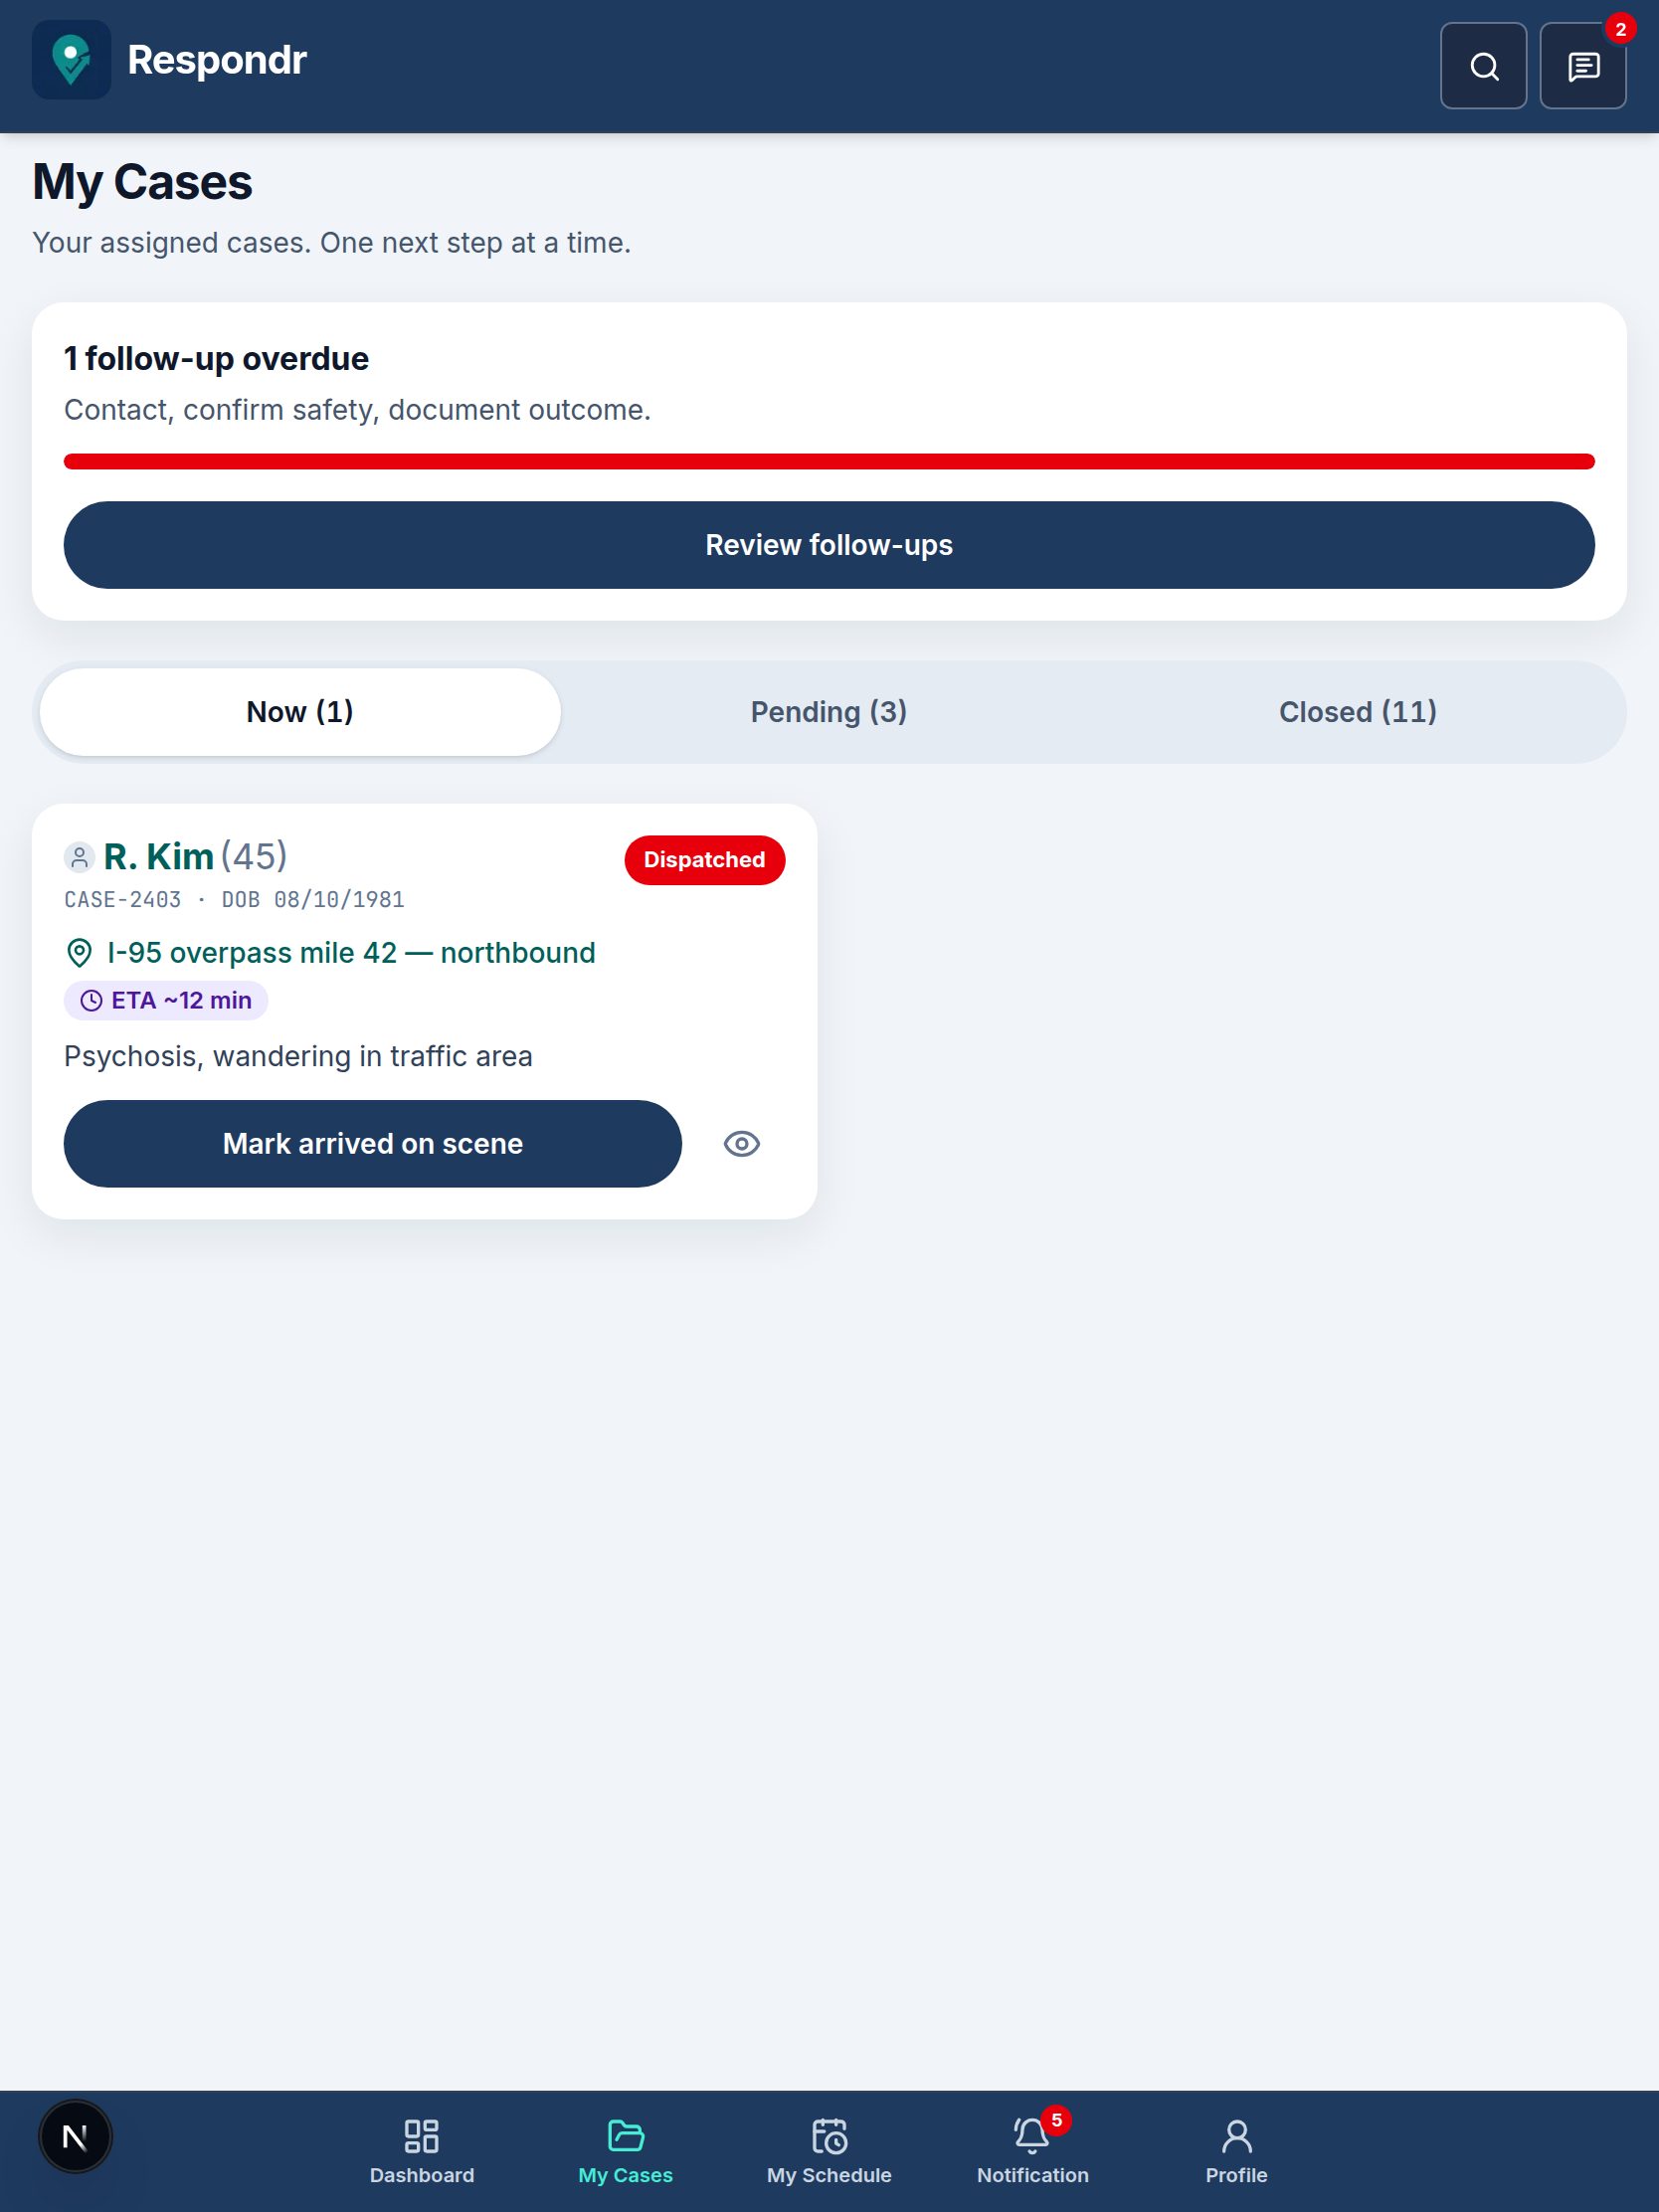
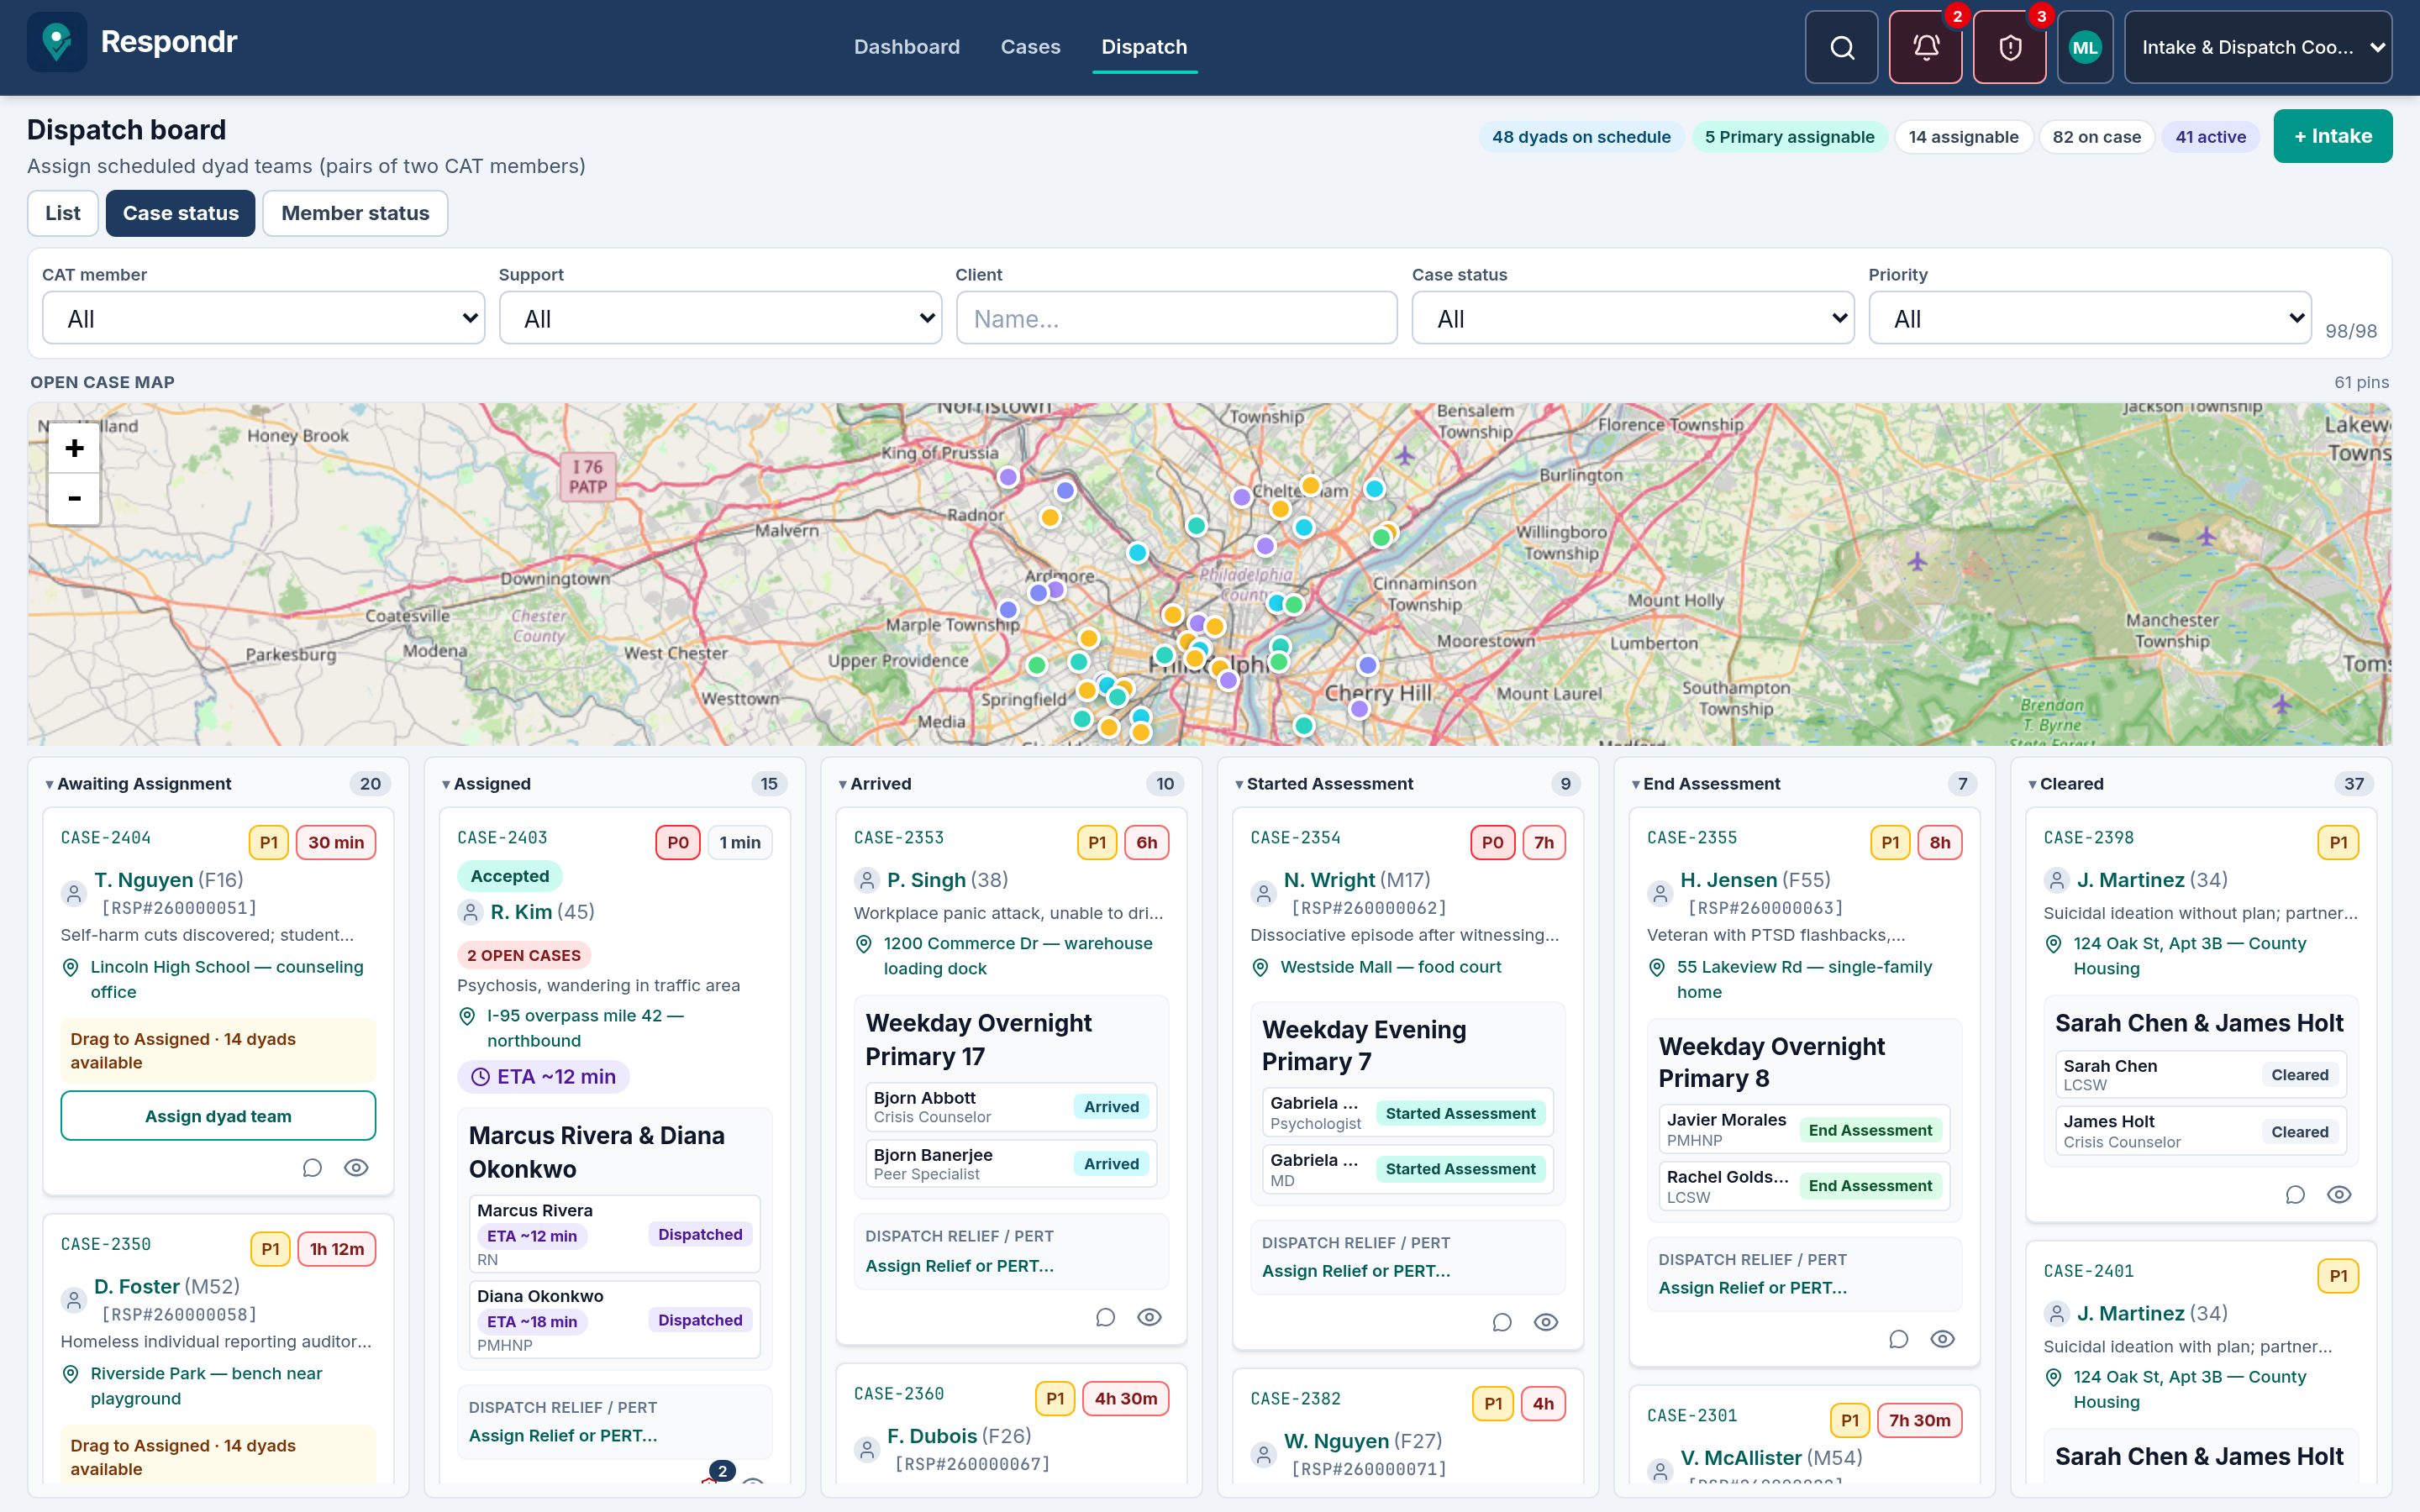
Accept dispatch captures where the CAT member is. Each person gets their own drive-time estimate. The fastest ETA sits next to the incident address until someone marks Arrived on scene — so dispatch and the rest of the CAT team can see who is closest.
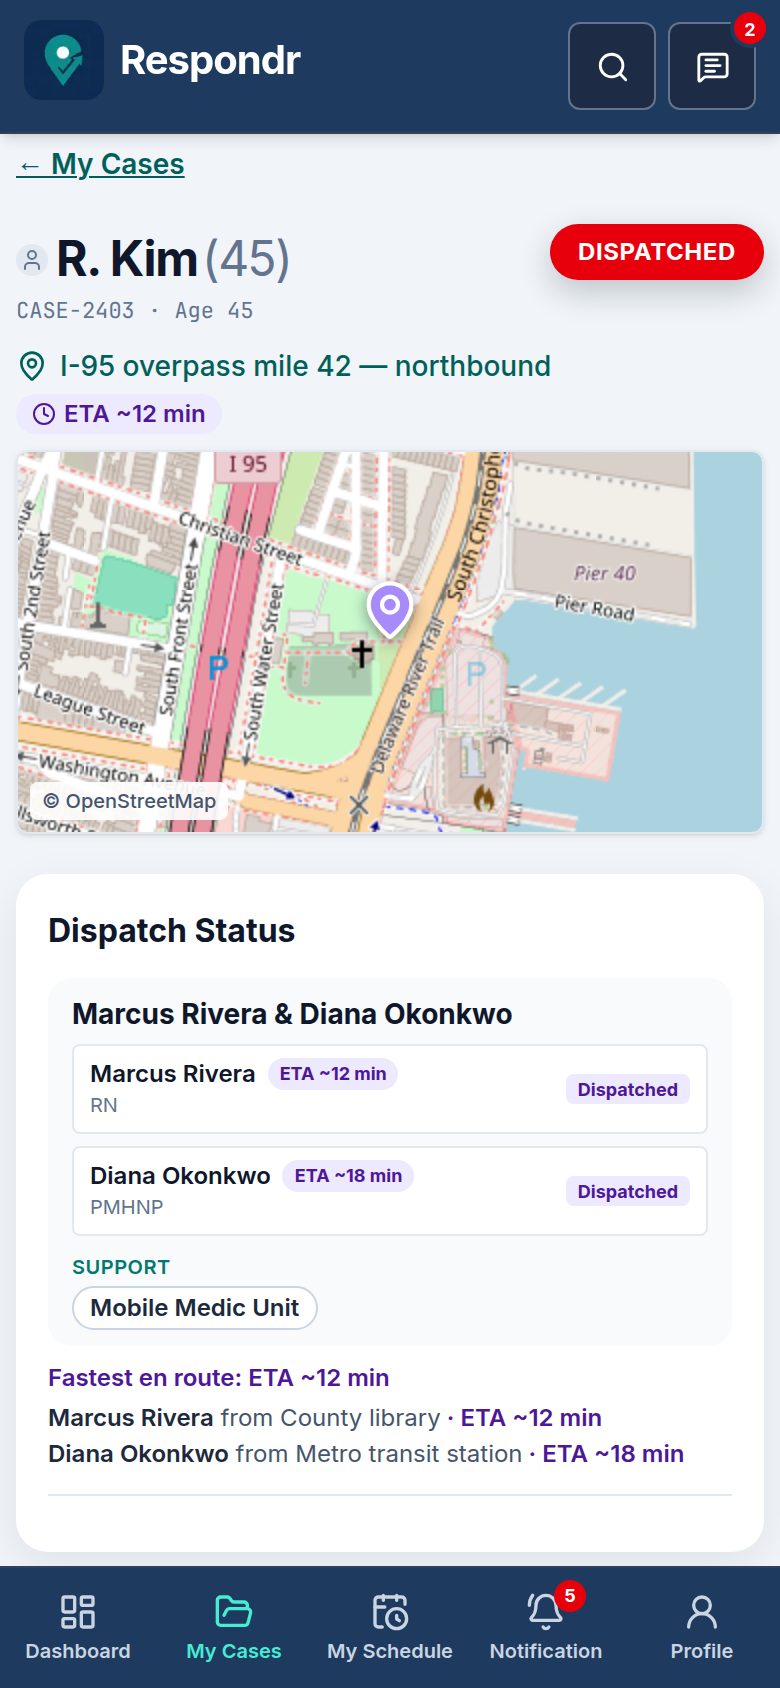
Case detail opens a full-width map of the scene under Location. Tap the pin to open Apple or Google Maps for turn-by-turn. Tablet gives the same record more room without a desktop kanban.
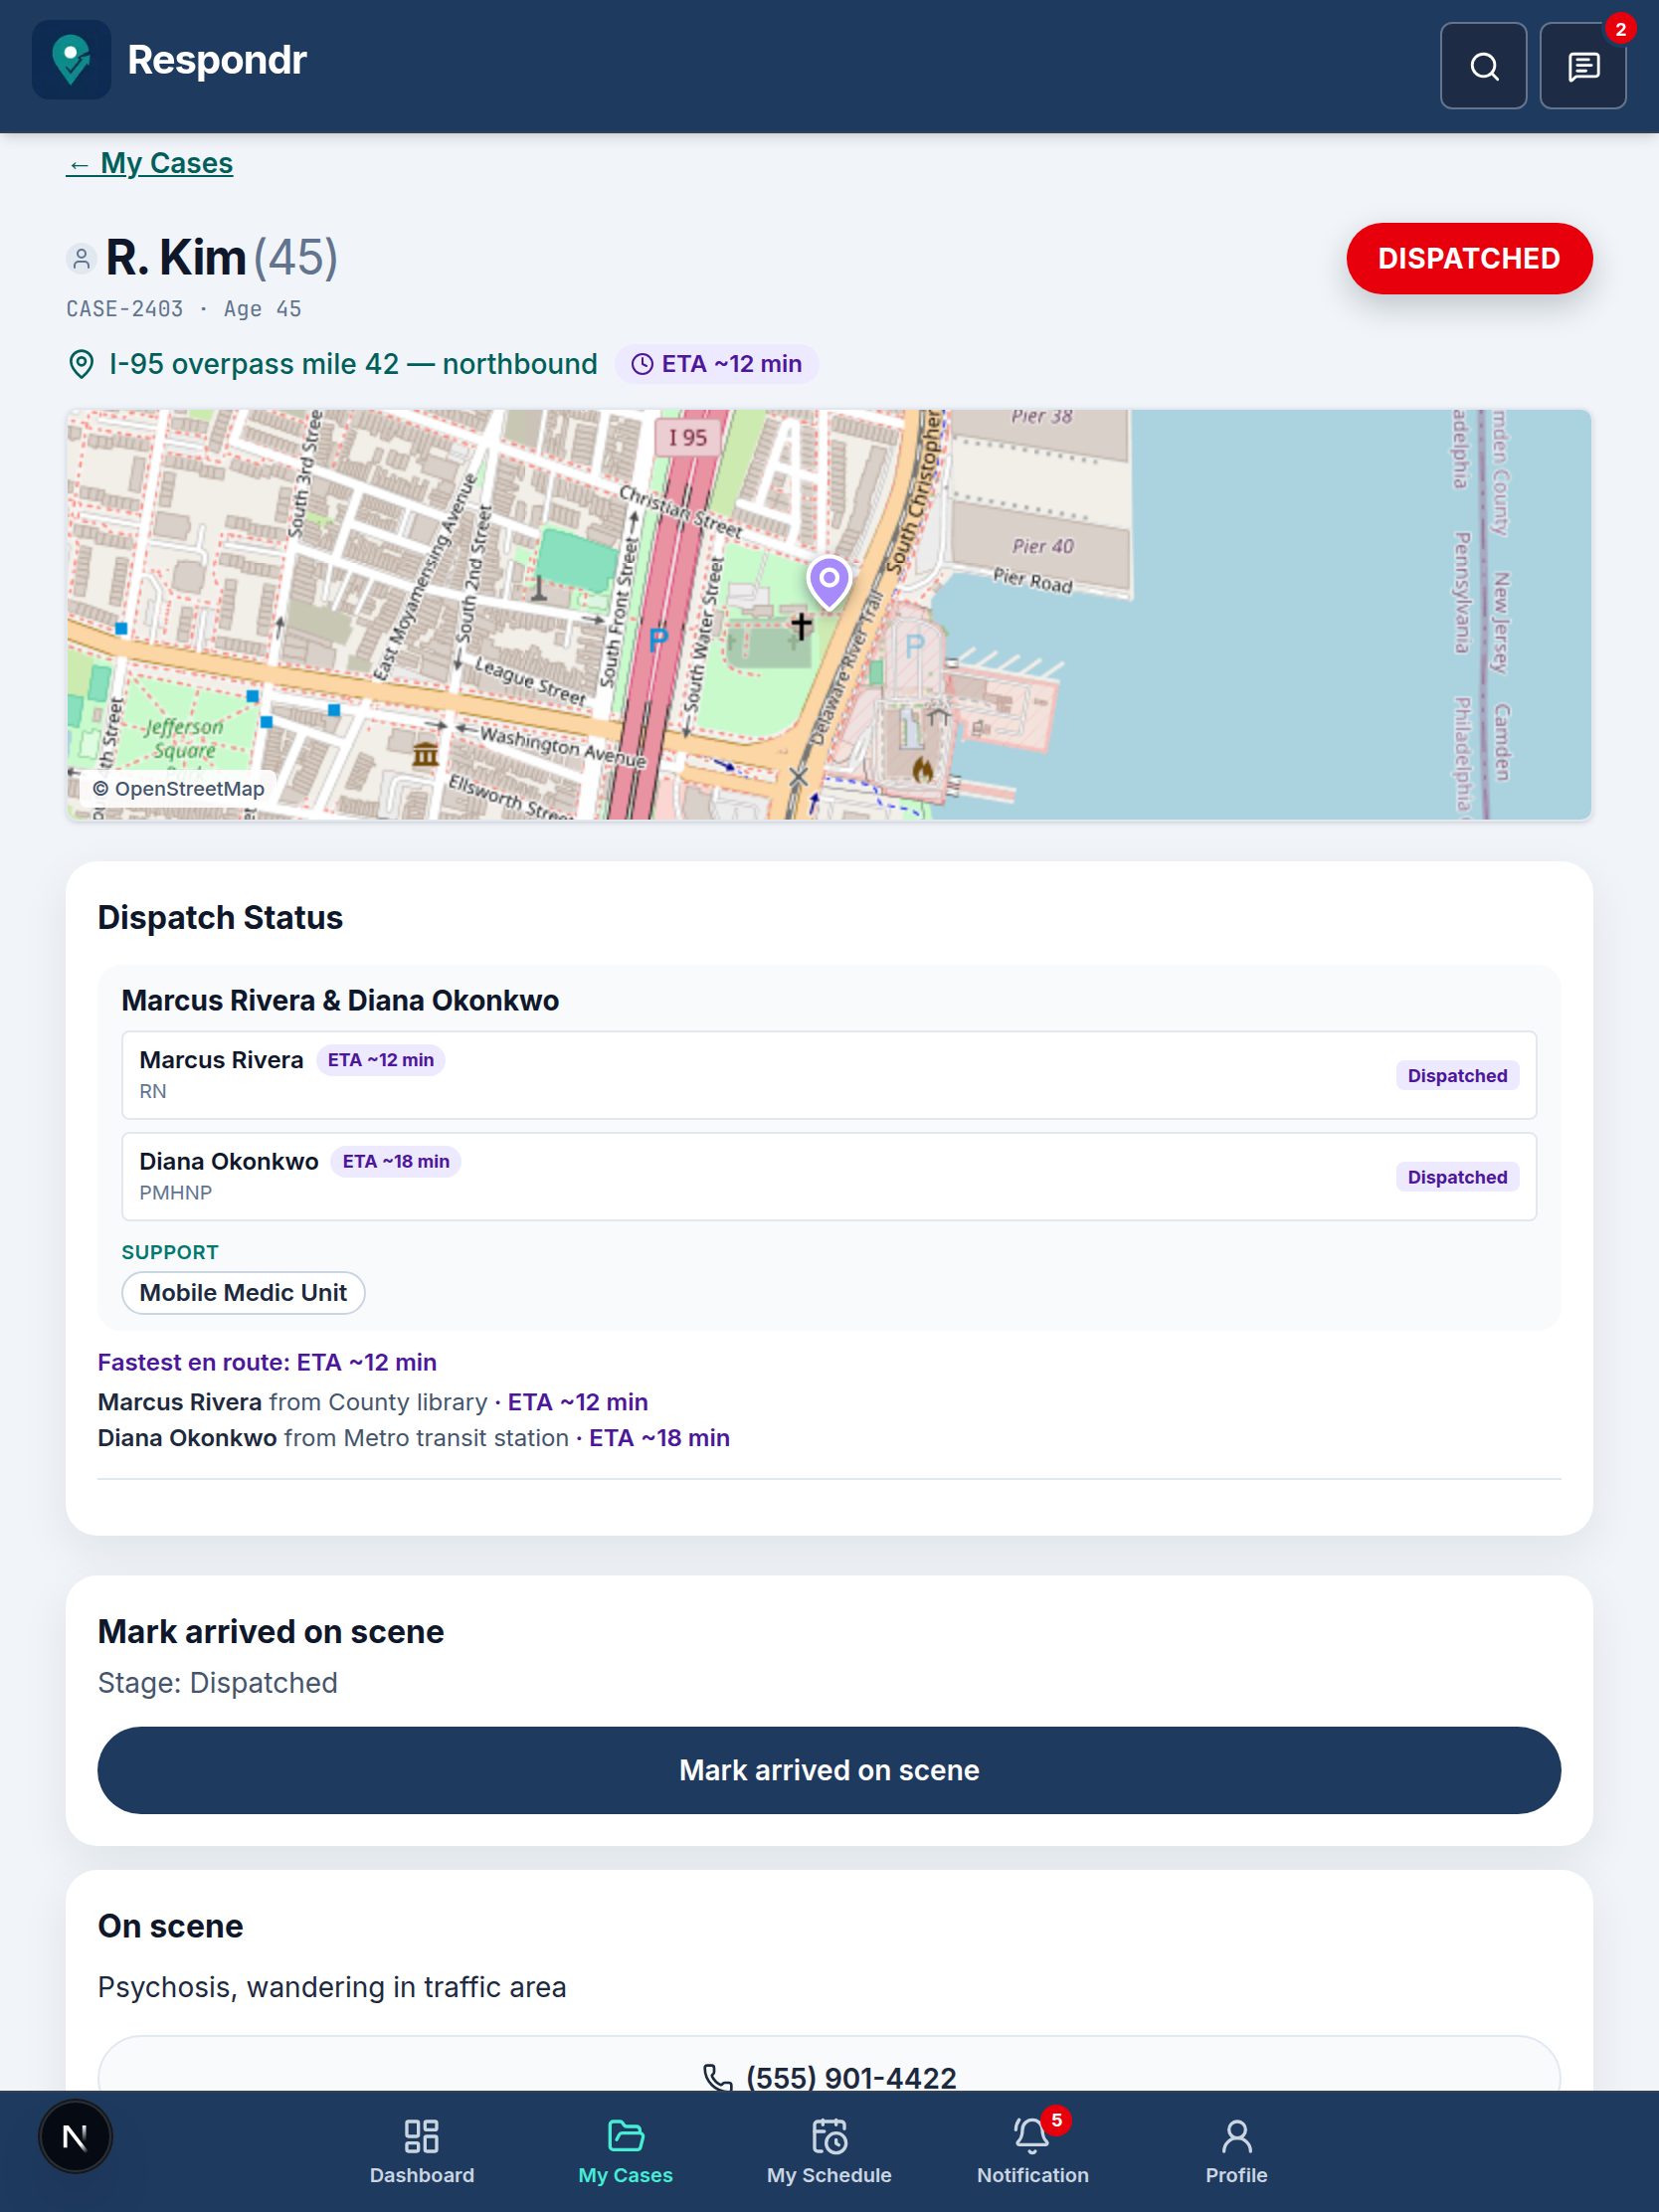
Watch how Respondr moves someone from first contact through CAT, placement into a bed or SUD stay, and into care coordination — without losing the episode.
Step 1 of 6
988 or county line — specialist opens a case in real time.
Crisis owns tonight’s emergency. Bed and SUD own the stay. Care Coordination owns the thread. “We faxed it” is not a status — Accepted, Waitlisted, Admitted, or Declined with a reason.
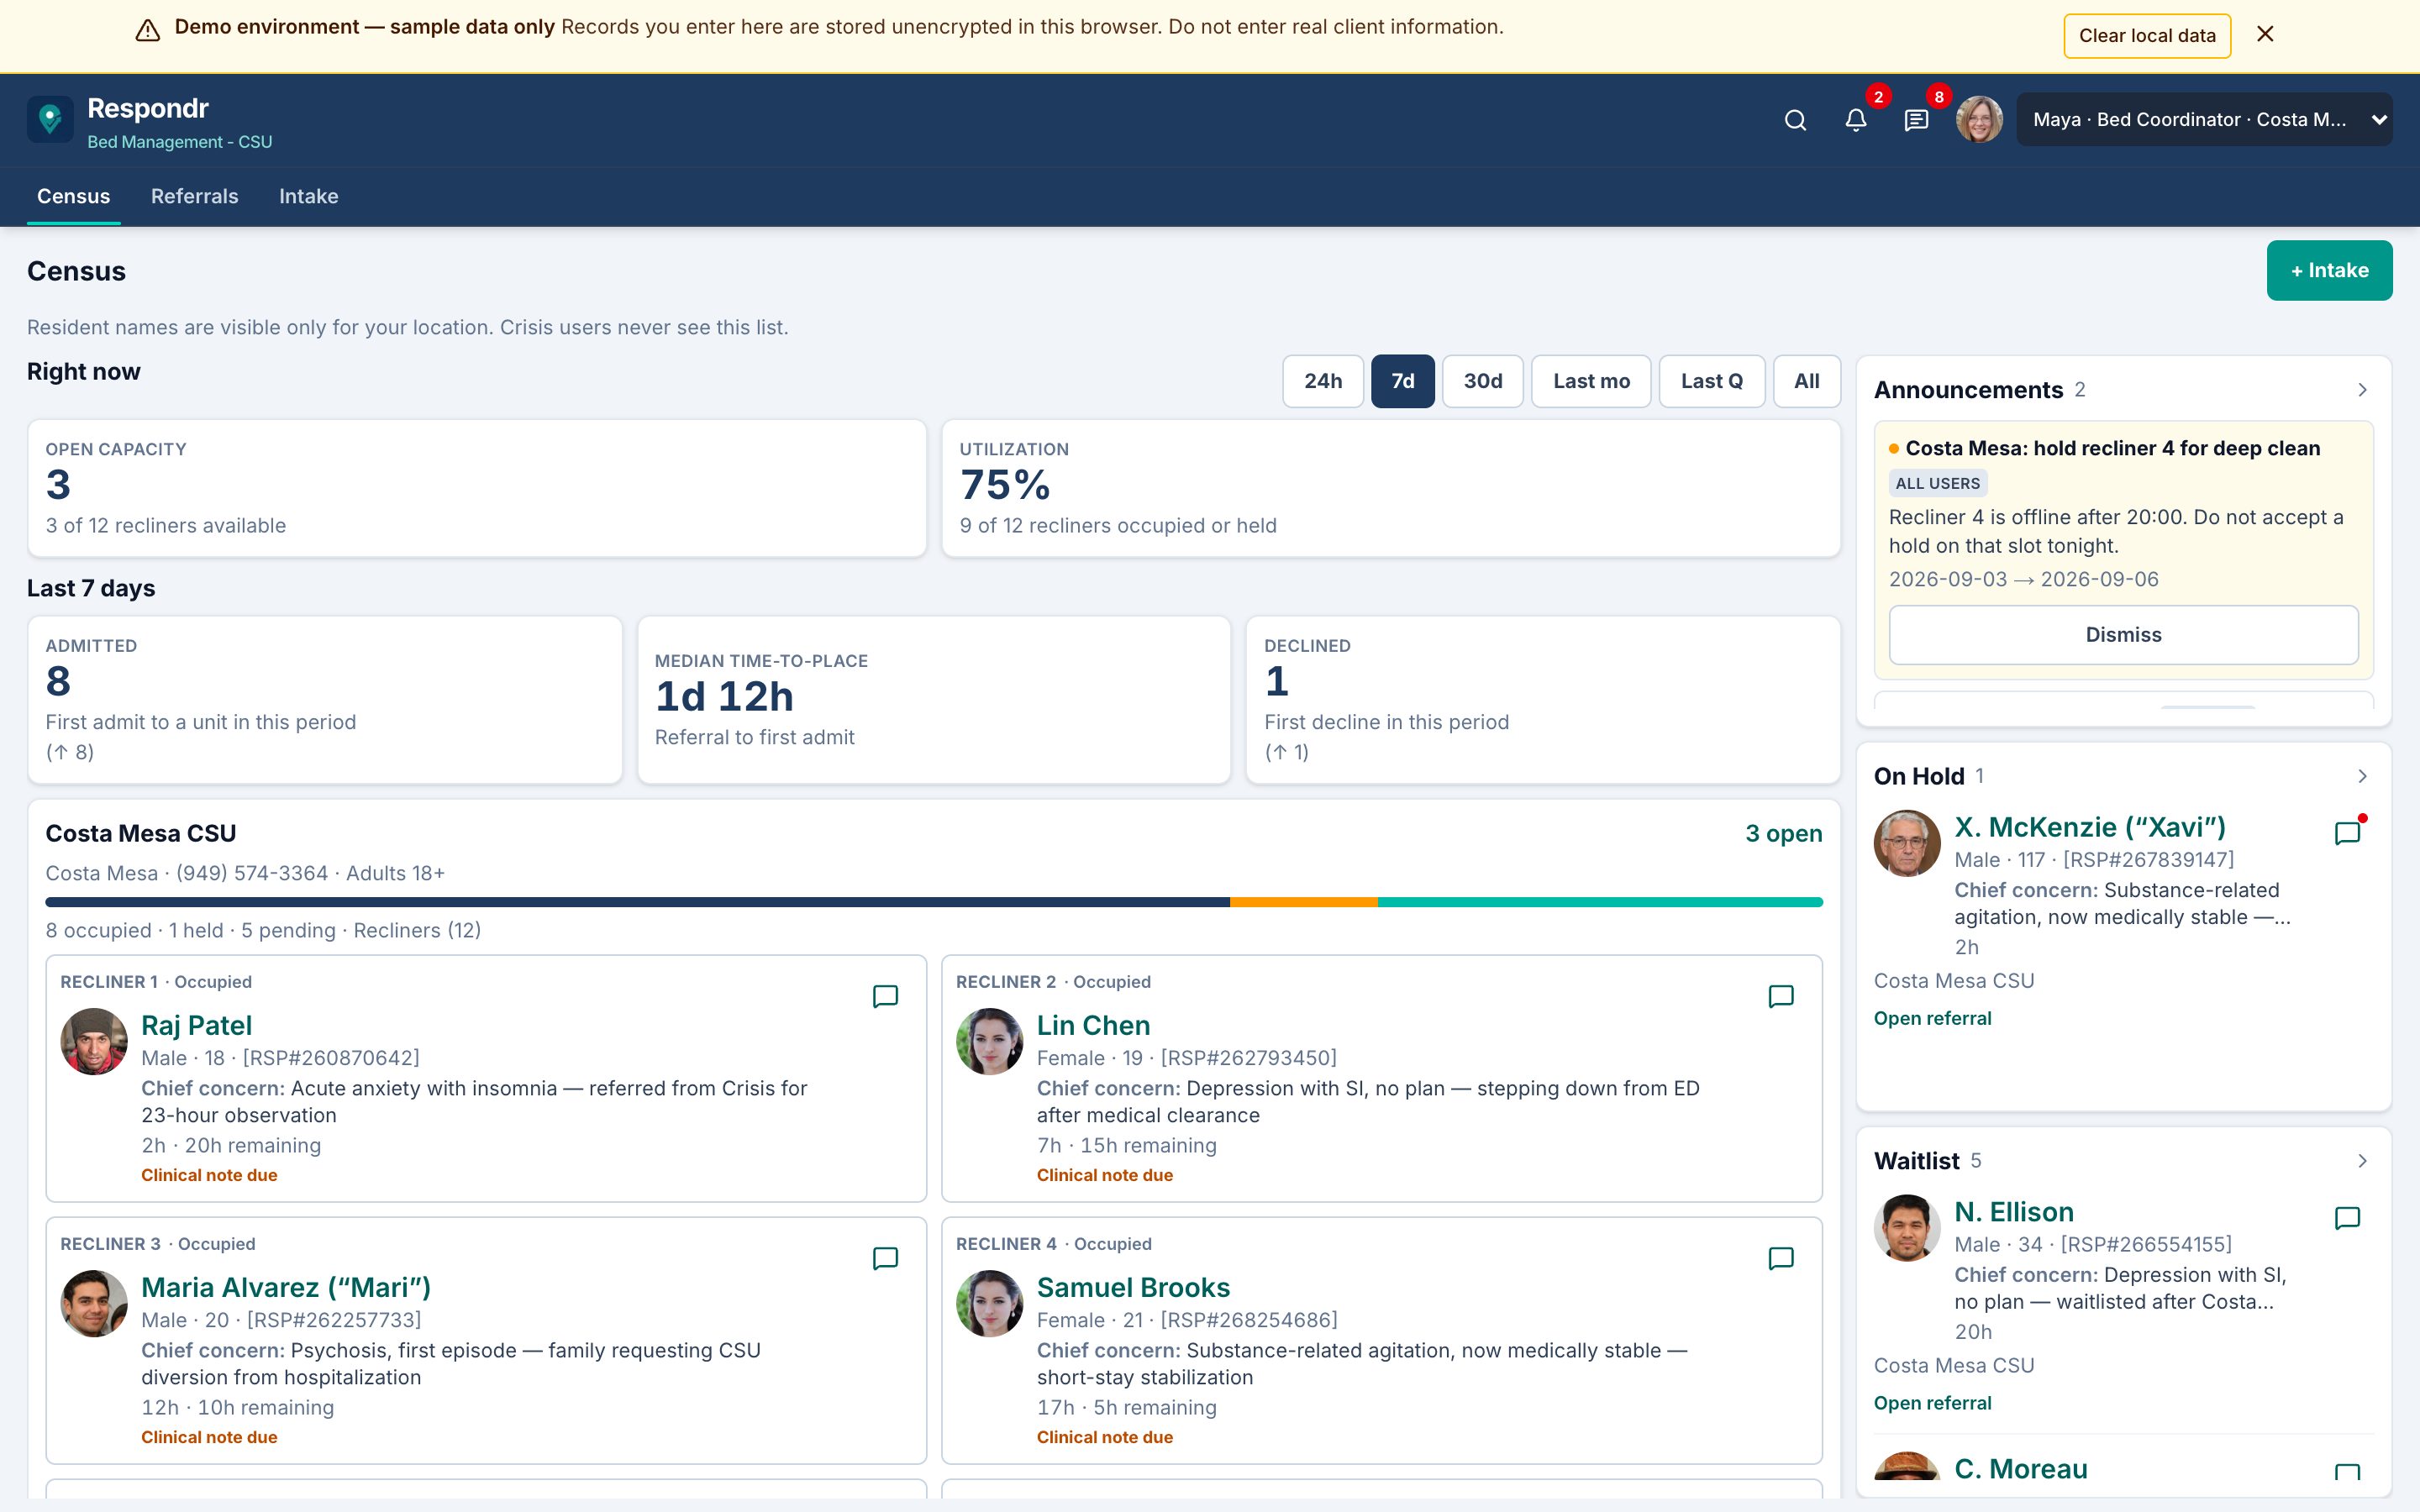
Tonight’s bed
Bed Management shows open capacity, occupied names, holds, and waitlist rails for CSU, CRS, and in-home slots. Crisis sends a closed-loop packet; accepting a referral is not the same as admitting to a bed.
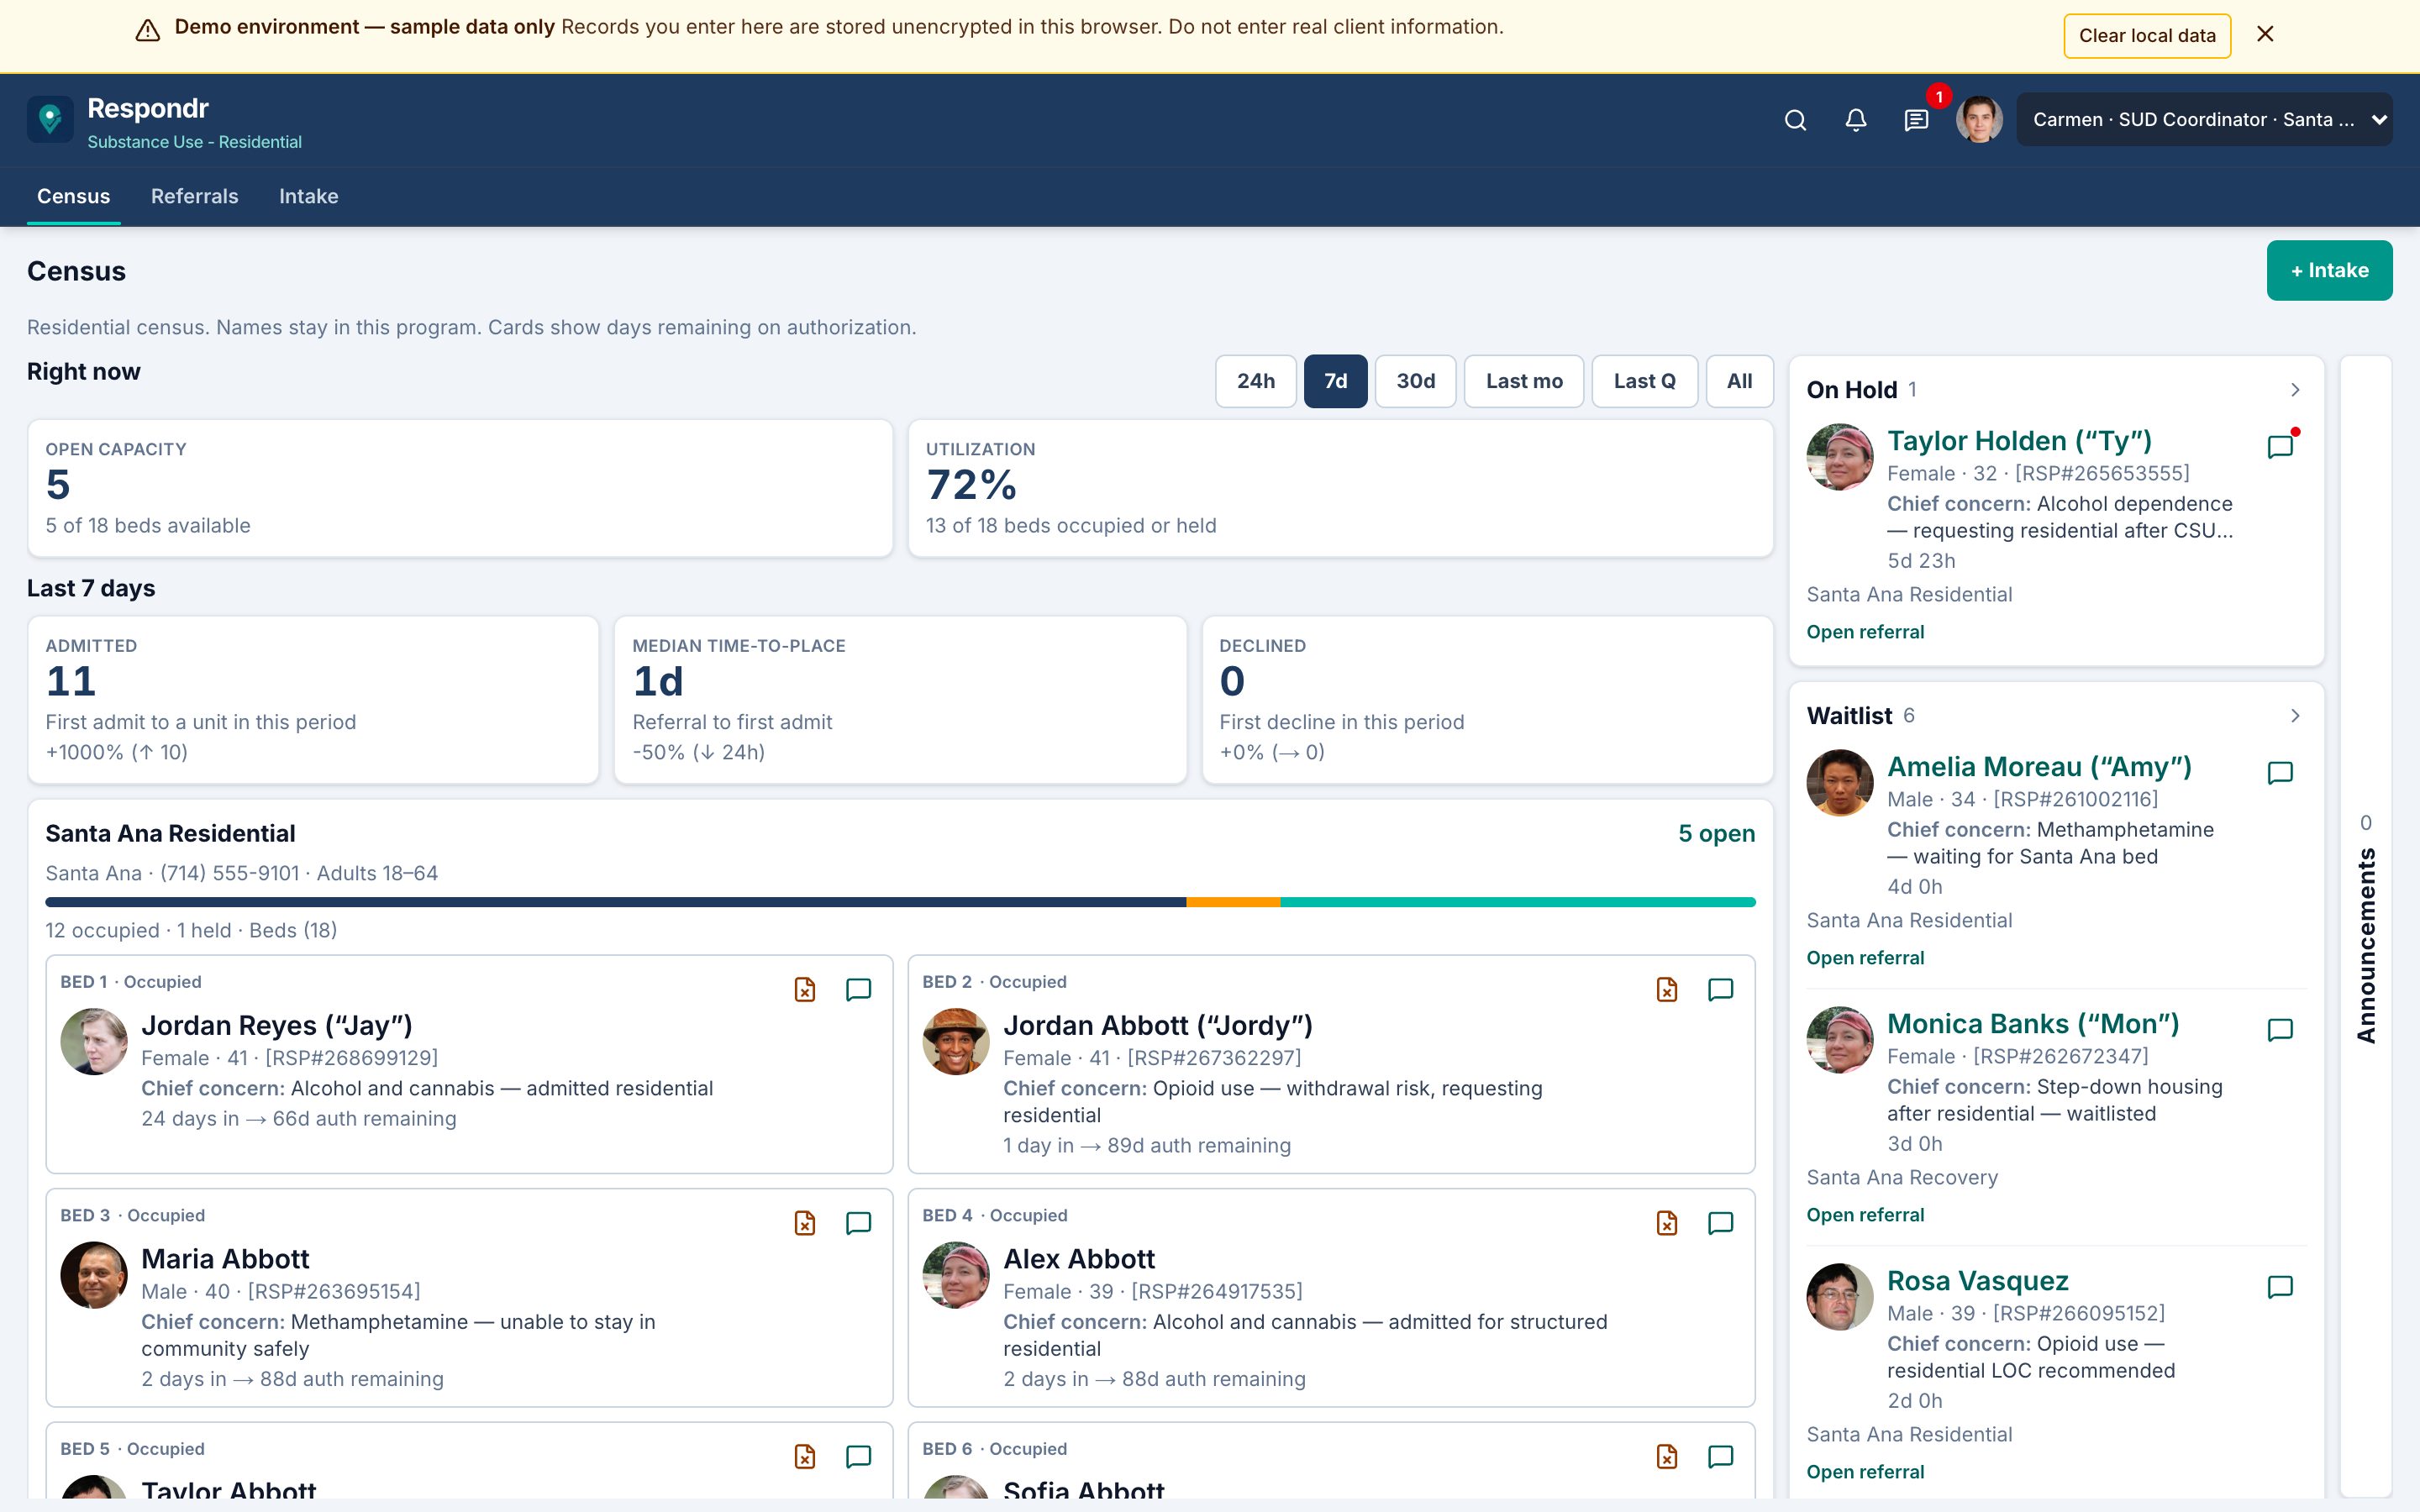
This treatment stay
Substance Use census tracks who is on the unit and how authorization days remain — so the stay, not just the referral fax, stays operational.
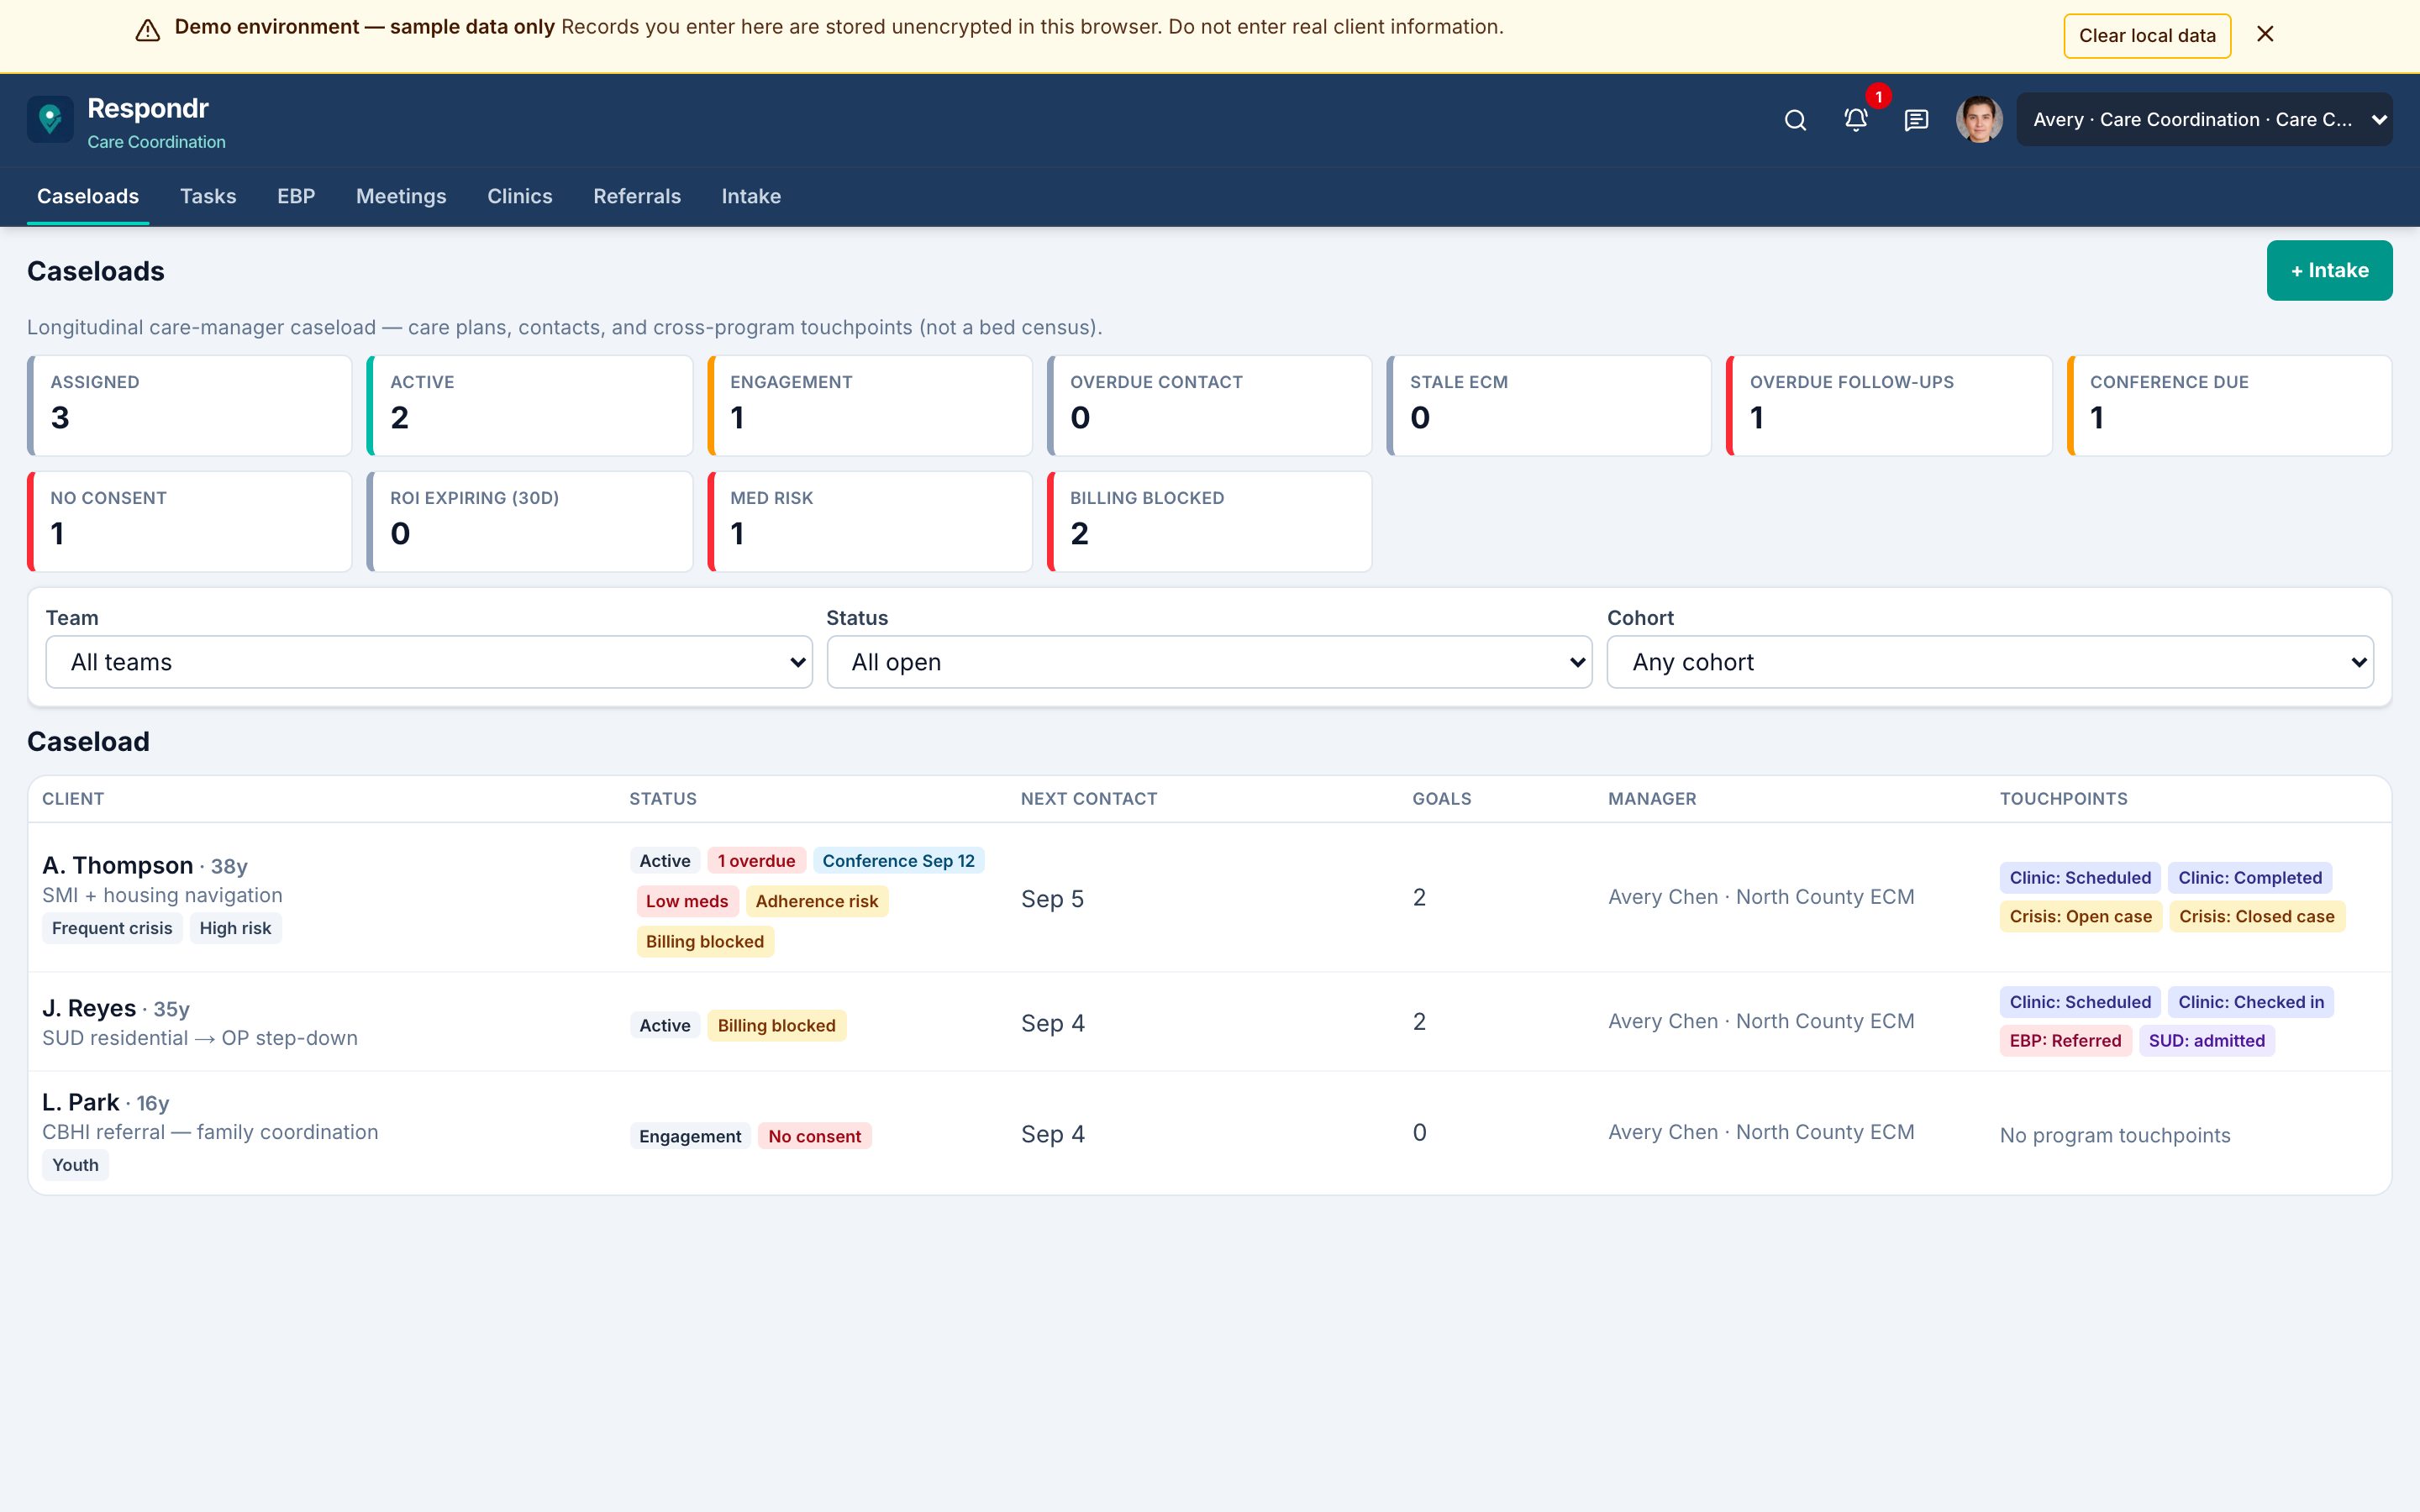
The months after
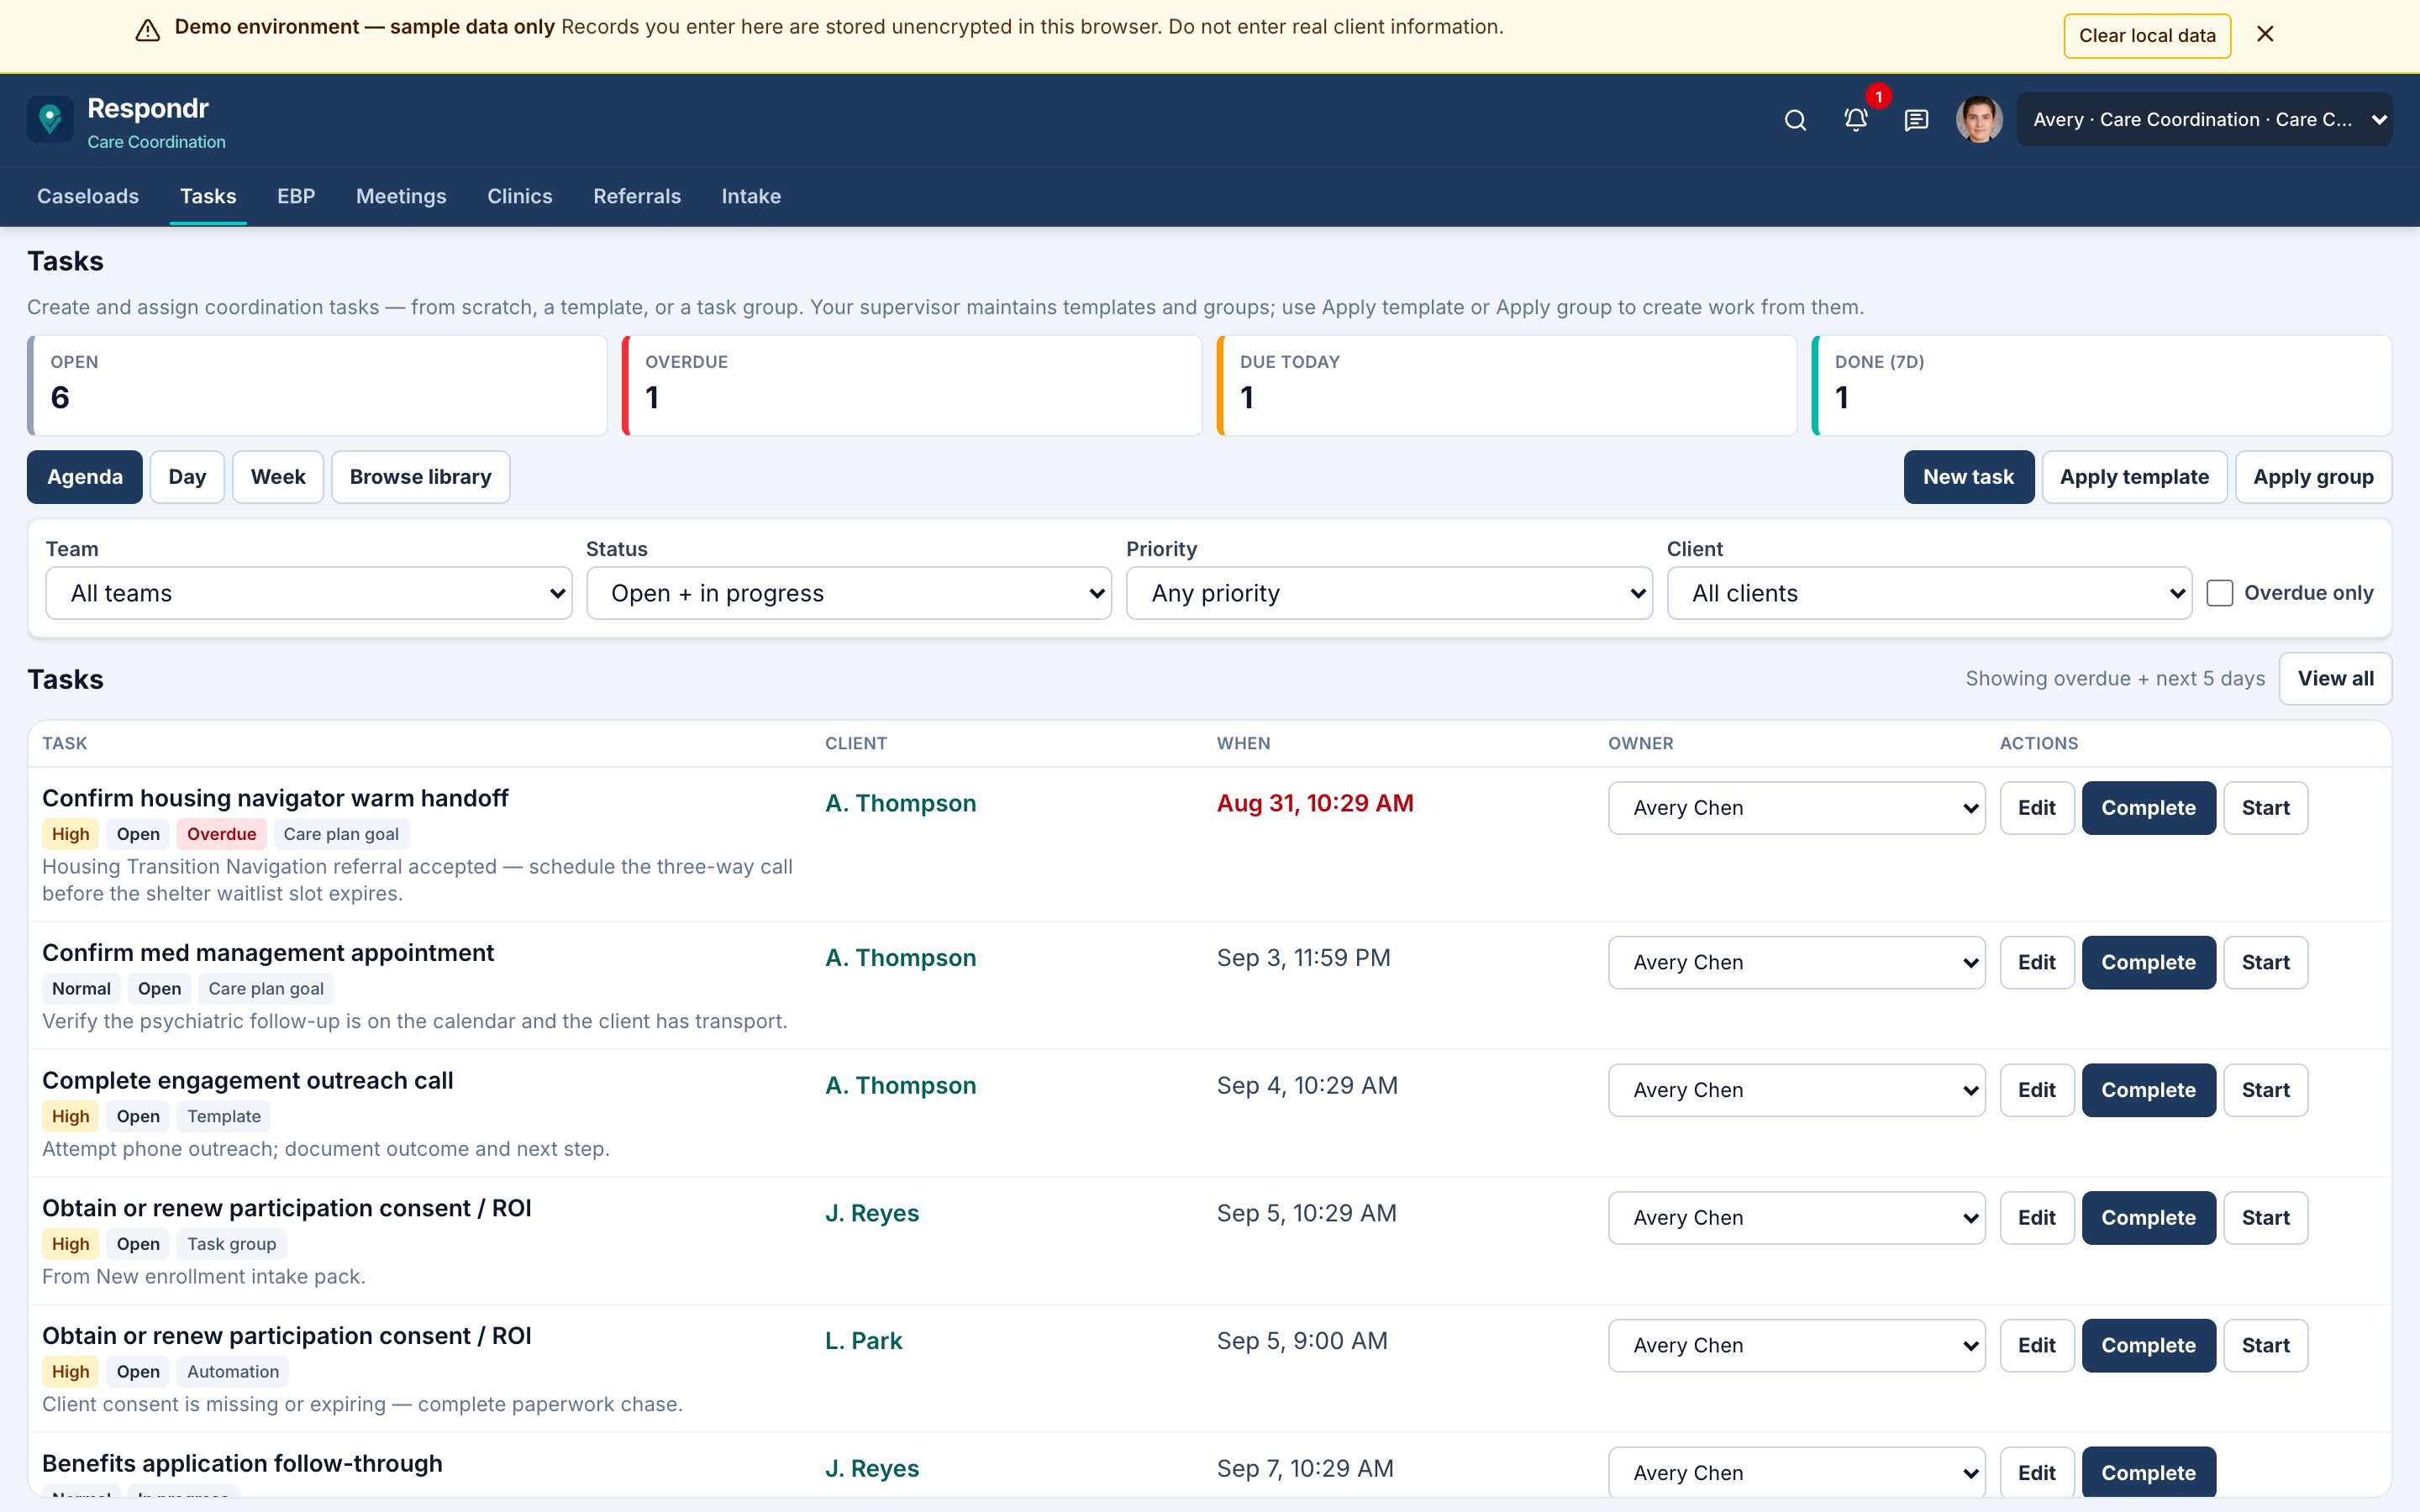
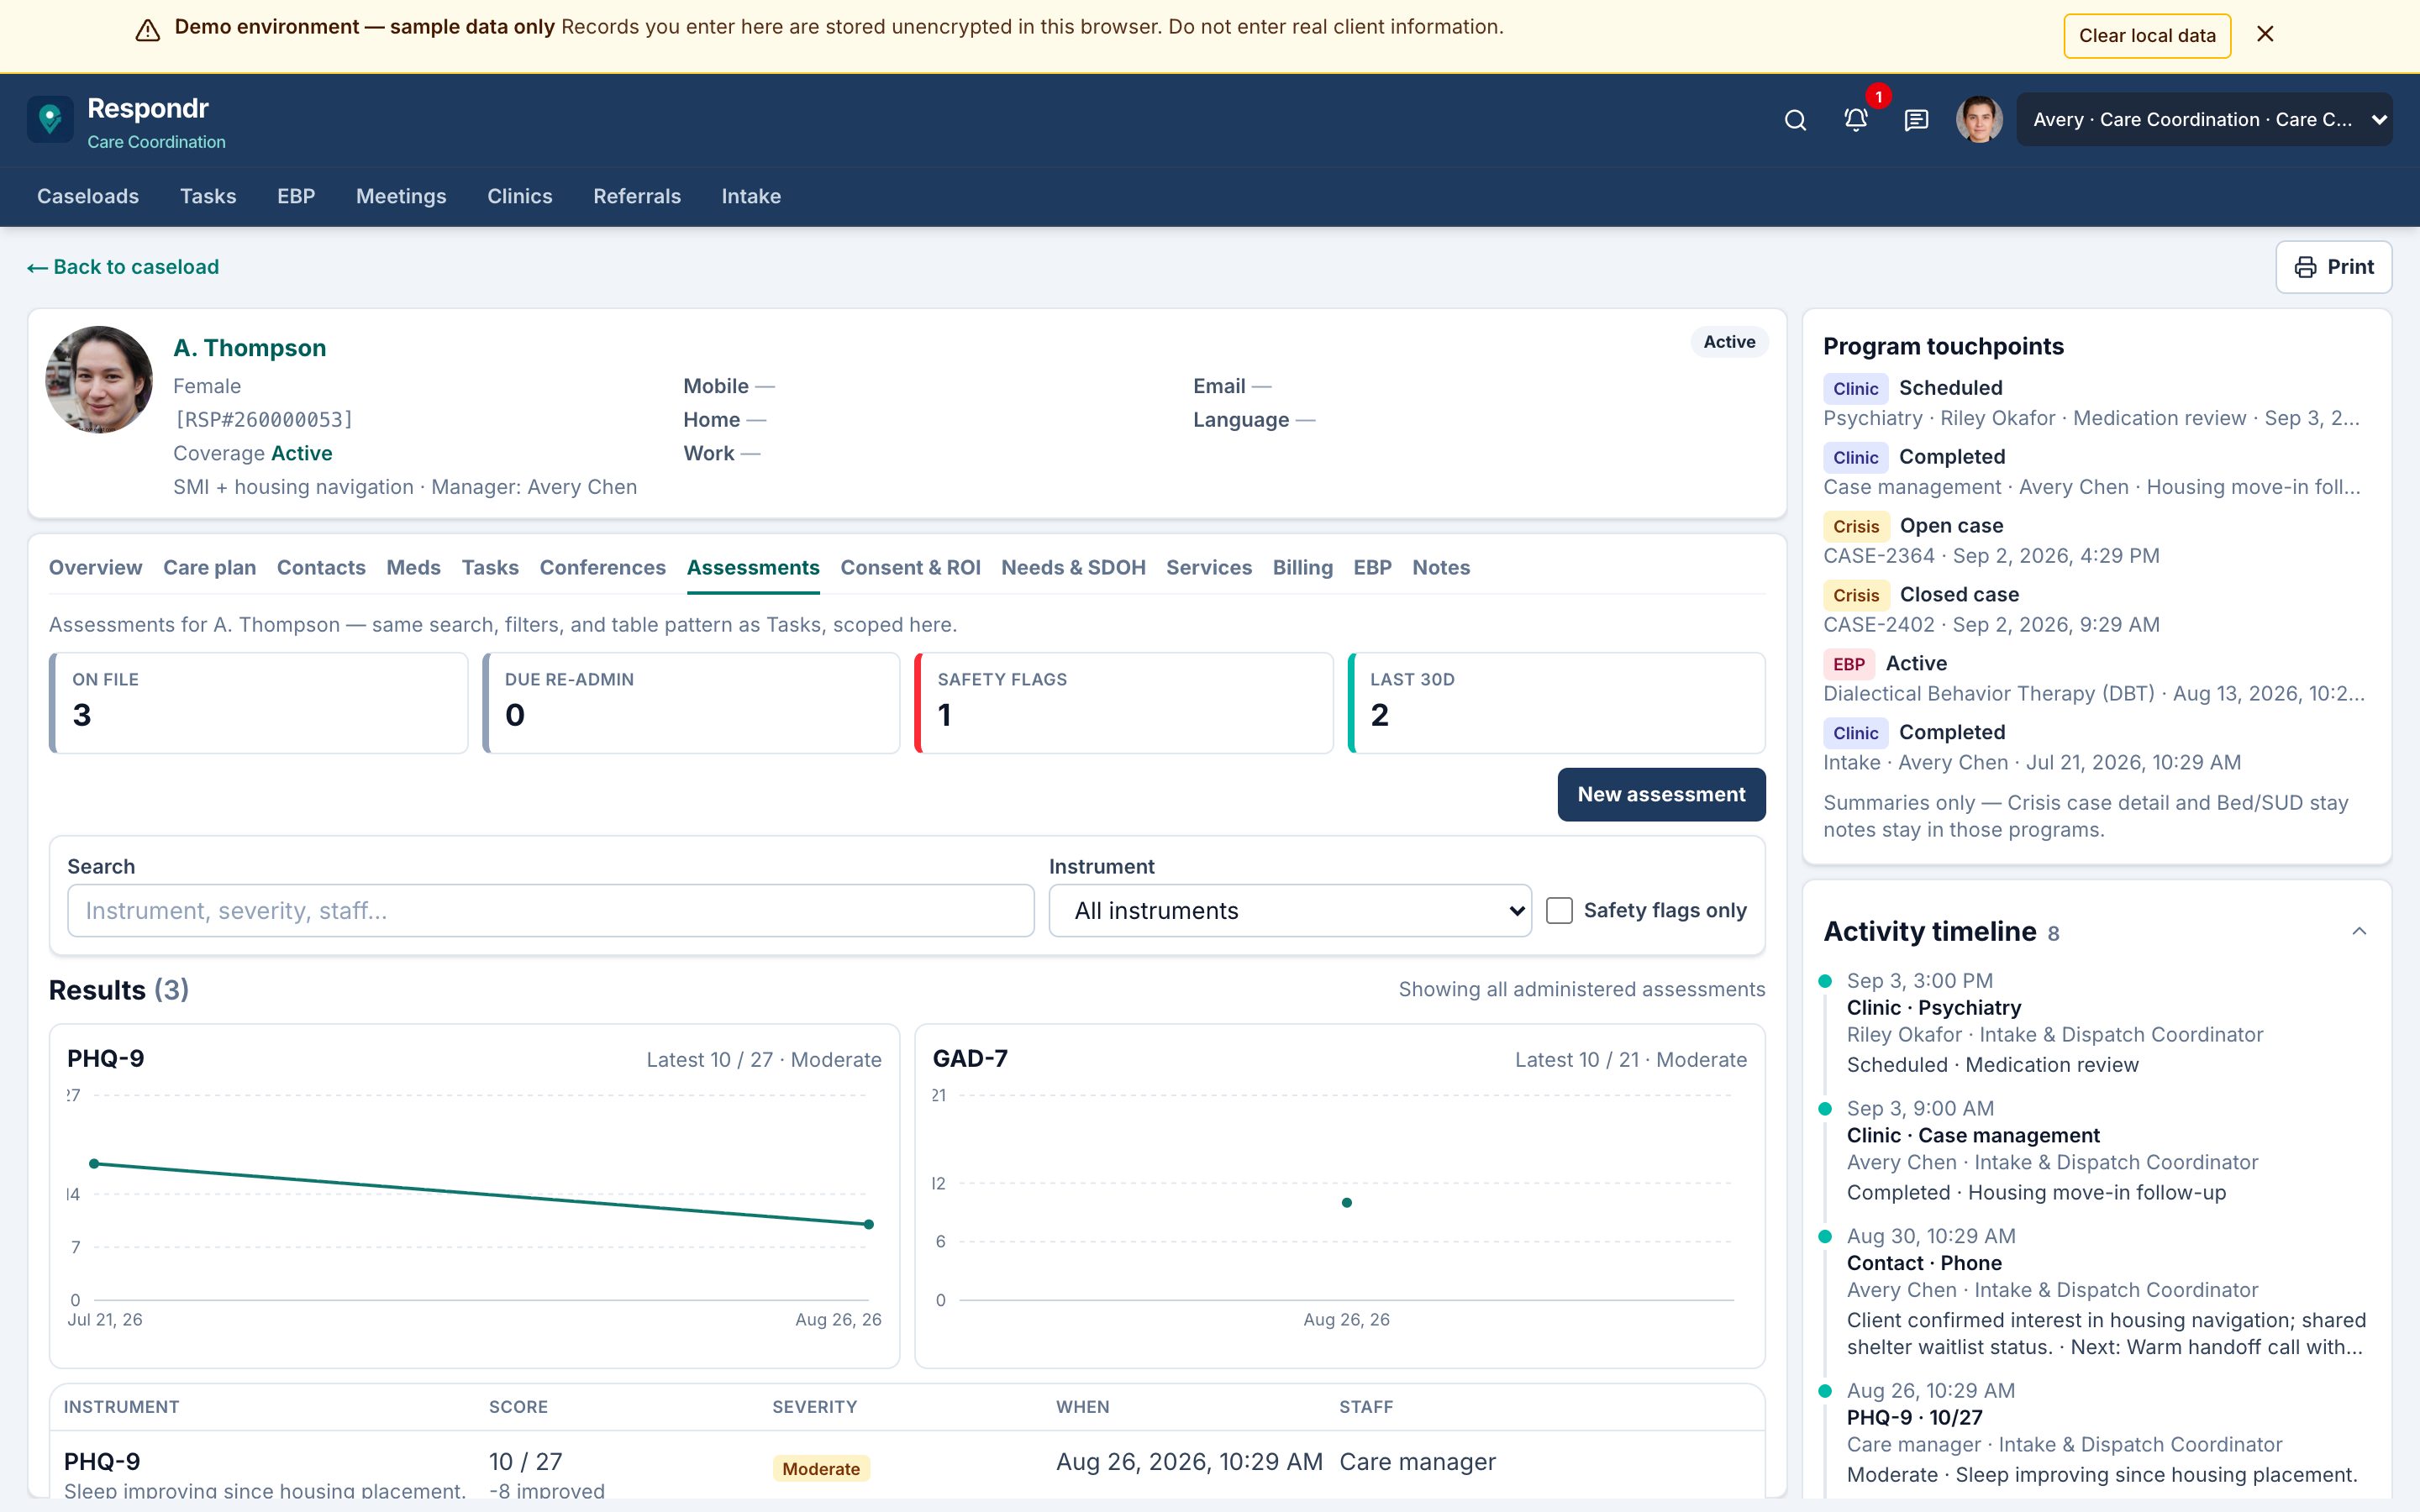
Care Coordination enrolls the person after crisis or discharge. Coordinators work overdue contacts, tasks, meds awareness, and assessments without opening CSU overnight notes or the crisis kanban.
Counties do not share one intake form or one bed policy. Share how your line, dispatch, placement, and care coordination actually work. We adjust the live demo in days — AI-assisted build is why that is fast, not what you are buying — then you walk the same thread on your rules.
Intake fields, CAT team vs solo, assign SLA, 72-hour follow-up, bed and SUD placement rules, and what “cleared” means on your team.
Workflow and seeds typically change in days — fields, SLAs, CAT statuses, resource list, census. HIPAA hosting, BAA, SSO, and EHR or 988-vendor integration are not a week; we say that up front.
Same continuum — Crisis, Bed, SUD, and Care Coordination personas — on boards that follow your protocol, not a generic county template.
Coordinators, CAT, and supervisors get a header bell for what they need to do, and a case thread so the team does not leave the record.
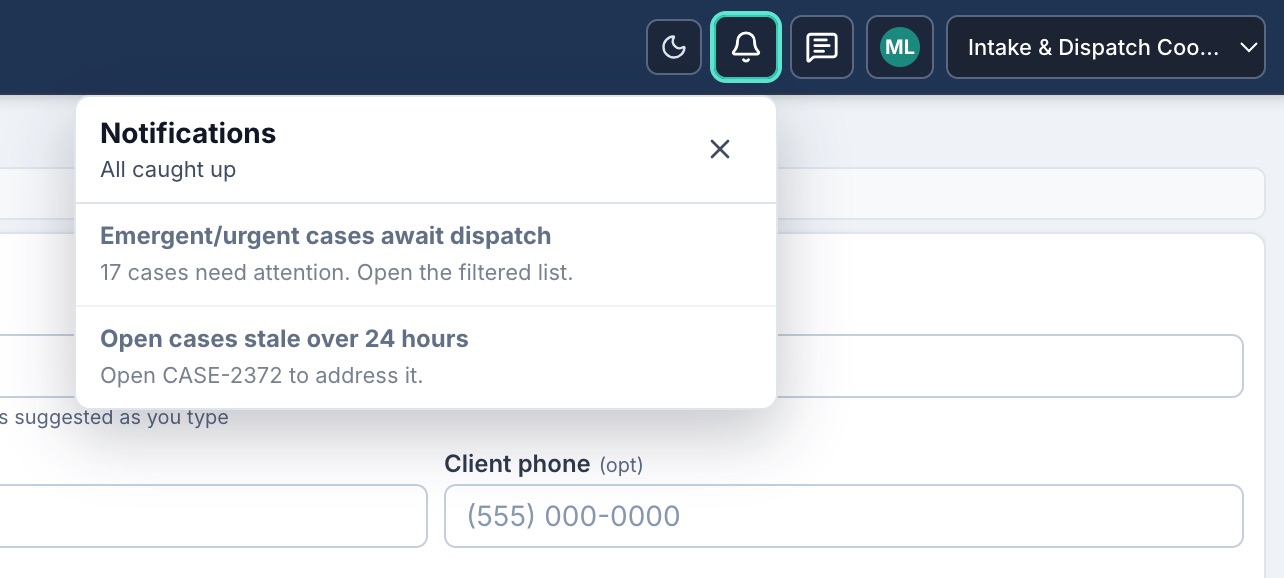
Role-scoped items: P0/P1 waiting for dispatch, overdue 72-hour follow-ups, pending warm handoffs, PTO to review, and staffing gaps. Click through to the exact case, filter, or scheduler screen.
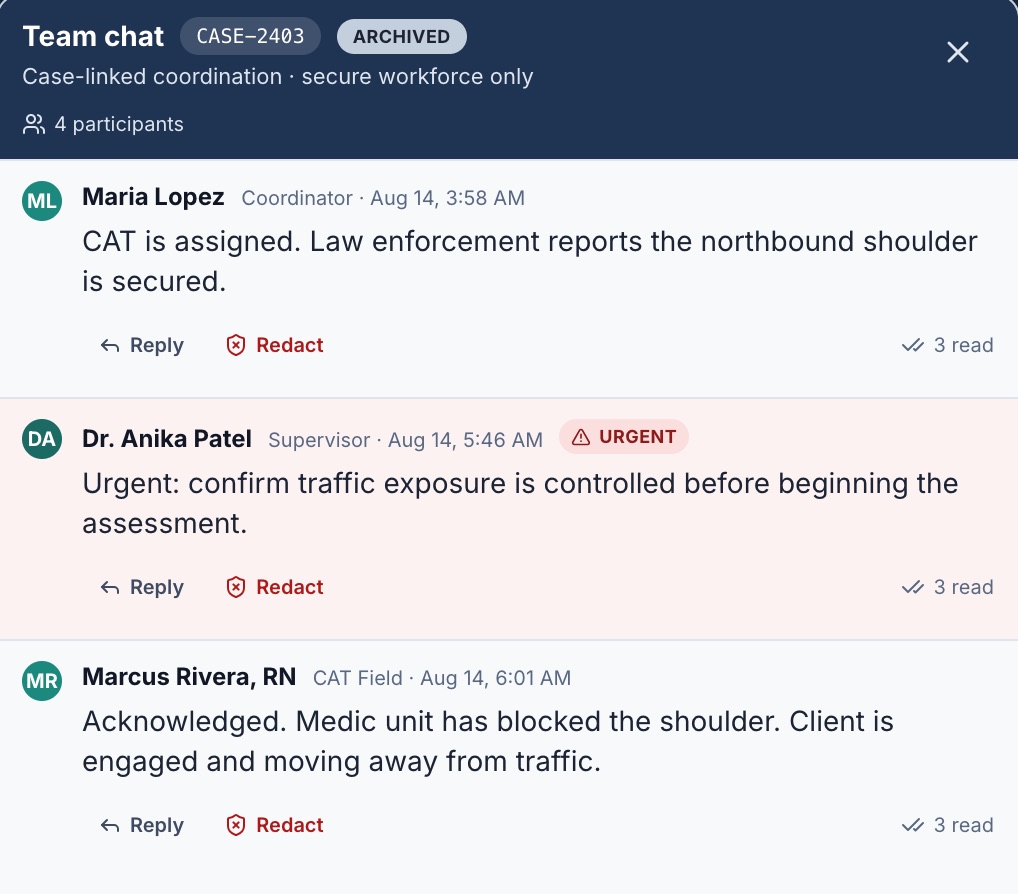
Each case keeps a team thread with unread counts in the header. Field and dispatch stay aligned on arrival, assessment, and handoff without a side channel.
No. Respondr is operations software for crisis, bed management, substance use stays, and care coordination. It complements your clinical systems rather than replacing them — programs keep their own notes; the platform keeps status, capacity, and the person’s thread.
City mobile crisis units, county behavioral health (including Crisis Now / 988 call centers), and state or regional programs that need one intake-to-dispatch thread across jurisdictions — plus the bed, SUD, and care coordination teams that receive those people. The same workflow scales from a municipal CAT team to a multi-county continuum.
Yes. CAT My Cases is built for phones and tablets: a single-column phone home, a two-column tablet grid, an incident map on each assignment, and an ETA next to the address after a team member accepts dispatch.
Each case has a team chat thread. A header bell lists role-scoped work — P0/P1 waiting for dispatch, overdue follow-ups, pending warm handoffs, and PTO to review — and opens the exact screen.
Dispatchers assign scheduled Primary CAT teams from the board or intake. Relief and PERT cover backup and escalation; per-member status shows who has arrived, started assessment, or cleared.
The supervisor dashboard shows Crisis now (open, unassigned, P0/P1), stale cases (24h+), team utilization, and PTO. Notifications and the CAT team scheduler keep staffing and caseload in the same loop.
Request a demo on this site. The next step is a live walkthrough with our team — crisis intake and CAT, then bed or SUD census and care coordination when that matches your continuum. You can book that time from the confirmation page. We email a time-limited access code after we review the request; the site does not generate a code automatically.
Workflow and demo seeds — intake fields, SLAs, CAT statuses, follow-up rules, resource lists — typically change in days or a couple of weeks. HIPAA production hosting, a BAA, SSO/IdP, and EHR or 988-vendor integration are not a week; those follow a later production conversation. The public demo uses local browser storage only.
The production platform is designed for HIPAA-aligned hosting with encryption, RBAC, and audit logs. This demo uses local browser storage only and is opened with a time-limited access code.
Yes. After crisis, closed-loop referrals go to Bed Management (CSU, CRS, in-home) or Substance Use (residential, detox, and related stays). Receiving staff accept, waitlist, or decline with a reason — Accept is not Admit — and live census shows capacity and the stay clock.
Care Coordination is the months after the incident: a caseload of people, care plan, outreach tasks, meds awareness, and assessments — not tonight’s dispatch board. Enrollment is intentional; crisis and stay documentation stay in their programs.
Walk the full thread: crisis intake and CAT dispatch, bed or SUD census, then a care coordinator’s caseload. Request a demo and we'll email you an access code after we review your request, then pick a persona.